
EMR Integration ROI: What You Can Actually Count
EMR integration ROI sorted into three tiers: what you can count today, what needs a baseline first, and what is real but will never be a defensible...
6 min read

A patient fills in a form online, then gets handed a clipboard asking the same questions. Nothing broke. Two systems never spoke, and the patient is the one who noticed.
Most writing about integration treats this as an efficiency problem. Staff time, duplicate entry, wasted minutes.
It is also a scored one. Federal surveys measure whether information reached the patient, and federal programs now pay less when it does not.
There is a third thing, and it surprises people. The connection alone does not move the number. What moves it is somebody telling the patient to use it.
Below: where the experience actually breaks, what the rules now cost, and what to measure once it is working.
Start with how the term is defined. AHRQ treats patient experience as the range of interactions a patient has with the health system.
It also separates experience from satisfaction. Satisfaction asks whether expectations were met. Experience asks whether a specific thing happened.
That distinction matters for anyone buying software. A practice cannot engineer satisfaction. It can engineer whether the reminder arrived.
Two of the eight areas CAHPS surveys cover are care coordination and getting information. Both are questions about whether systems talked to each other.
Staff do not describe disconnection as a data problem. They describe it as the third phone call before a video visit starts. Every gap between systems becomes a person. Someone retypes the number, someone chases the form, someone explains the link.
That work is invisible in any report, which is why it survives budget cycles. Nobody has a line item called retyping.
Phone holds, instructions that arrive after the patient has left home, and a form posted the day before. A reminder built from scheduling data knows the visit type. One built from a spreadsheet does not, and sends parking instructions for a video call.
Prep is where the visit is won. A patient who arrives without the right paperwork turns a 15 minute slot into a 25-minute one.
Paper forms get transcribed, and transcription is where errors enter. An insurance card photographed at the desk gets typed in later, by whoever is free.
Patients read the clipboard as a signal. If the practice already has this information, being asked again says the systems do not talk. The fix is unglamorous. Intake completed before arrival, landing in the record without a second keystroke.
A clinician without outside records works from what the patient remembers. That is a worse exam, and the patient can tell. Results are the sharpest version. A finding sitting in an imaging system while the patient waits is a gap the patient experiences as silence.
Printed instructions get lost between the car and the kitchen. A message in a thread the patient already uses does not. Follow-up is also where the record matters most. Whoever takes the call at 9am should see what was sent at 5pm.
Digital access widens reach and narrows it at the same time, depending on who is holding the phone.
A patient without an app, a login or a data plan is not served by a portal. They are served by a link, a text, or a phone call. This argues for keeping more than one route open rather than retiring the old ones on a schedule.
Two directions matter. Reading the schedule tells the message who, when and where. Writing back puts the reply where the next person will look. Most tools do the first. Ask any vendor what happens to a patient's answer, and watch how long the pause is.
Trigger from appointment events rather than from a calendar job. Prep, reminder, arrival, survey, each hanging off a status the record already holds.
A shared inbox replaces the sticky note. Templates handle the questions that repeat every day, and the thread stays with the patient. The live version of this page claimed a 50% drop in phone volume. No source supports that figure, so it is gone.
What can be said is narrower. Calls fall when the answer is available without one, and every practice starts from a different number.
Reminders built on scheduling data confirm, cancel or reschedule. A cancellation two days out is a slot you can still fill. Be careful with the promised numbers here too. The 75% reduction this page used to claim has no study behind it.
Measure your own rate before and after. That figure is worth more than any vendor average, including ours.
Patient intake works best as registration, history, consents and insurance photos, completed on a phone and imported without retyping.
The test is whether anything lands in a staff inbox. A form that emails the front desk has moved the work rather than removed it.
Telehealth is where disconnection hurts most, because nobody can hand the patient a clipboard. Everything has to arrive before the visit starts. Troubleshooting is the symptom. We covered cutting telehealth support calls for CharmHealth staff, where the phone rings two minutes before the appointment.
Triage is the other use. Our piece on SMS-launched video triage in athenahealth covers routing low-risk patients before they travel.
Information blocking stopped being a vendor problem in 2024. A federal rule effective July 31, 2024 set out what it costs a provider.
A MIPS clinician referred by the Inspector General is treated as not a meaningful EHR user. That zeroes the Promoting Interoperability category. It carries about a quarter of the final score.
Hospitals lose three-quarters of the annual market basket increase. A critical access hospital drops from 101% of reasonable costs to 100%. Practices read those as billing rules. Patients experience the same conduct as nobody sending the records.
Seven numbers cover it. No-show rate, time to confirmation, and first response time on messages. Then check-in duration, survey completion, review volume, and the ratio of calls to texts.
Only one of those needs a new report. The rest are already sitting in systems the practice runs today.
Pick two and watch them weekly. Seven tracked monthly tells you less than two tracked often.
Curogram HighlightCurogram's Virtual Visits start from a text link, with no app and no portal login for the patient. The thread stays beside that patient's other messages, so staff work from one screen. Forms and replies write back rather than landing in an inbox. Which removes the support call before it happens. Nobody rings two minutes before the visit asking how to join. |
Map the visit end to end first, on one page, with the friction marked. Most teams find four or five points and recognize all of them.
Then connect scheduling, because every later step depends on knowing the visit type. Reminders, intake, and telehealth all read from it.
Digitize intake next, then telehealth links, then surveys. Each one is easier once the schedule is feeding it.
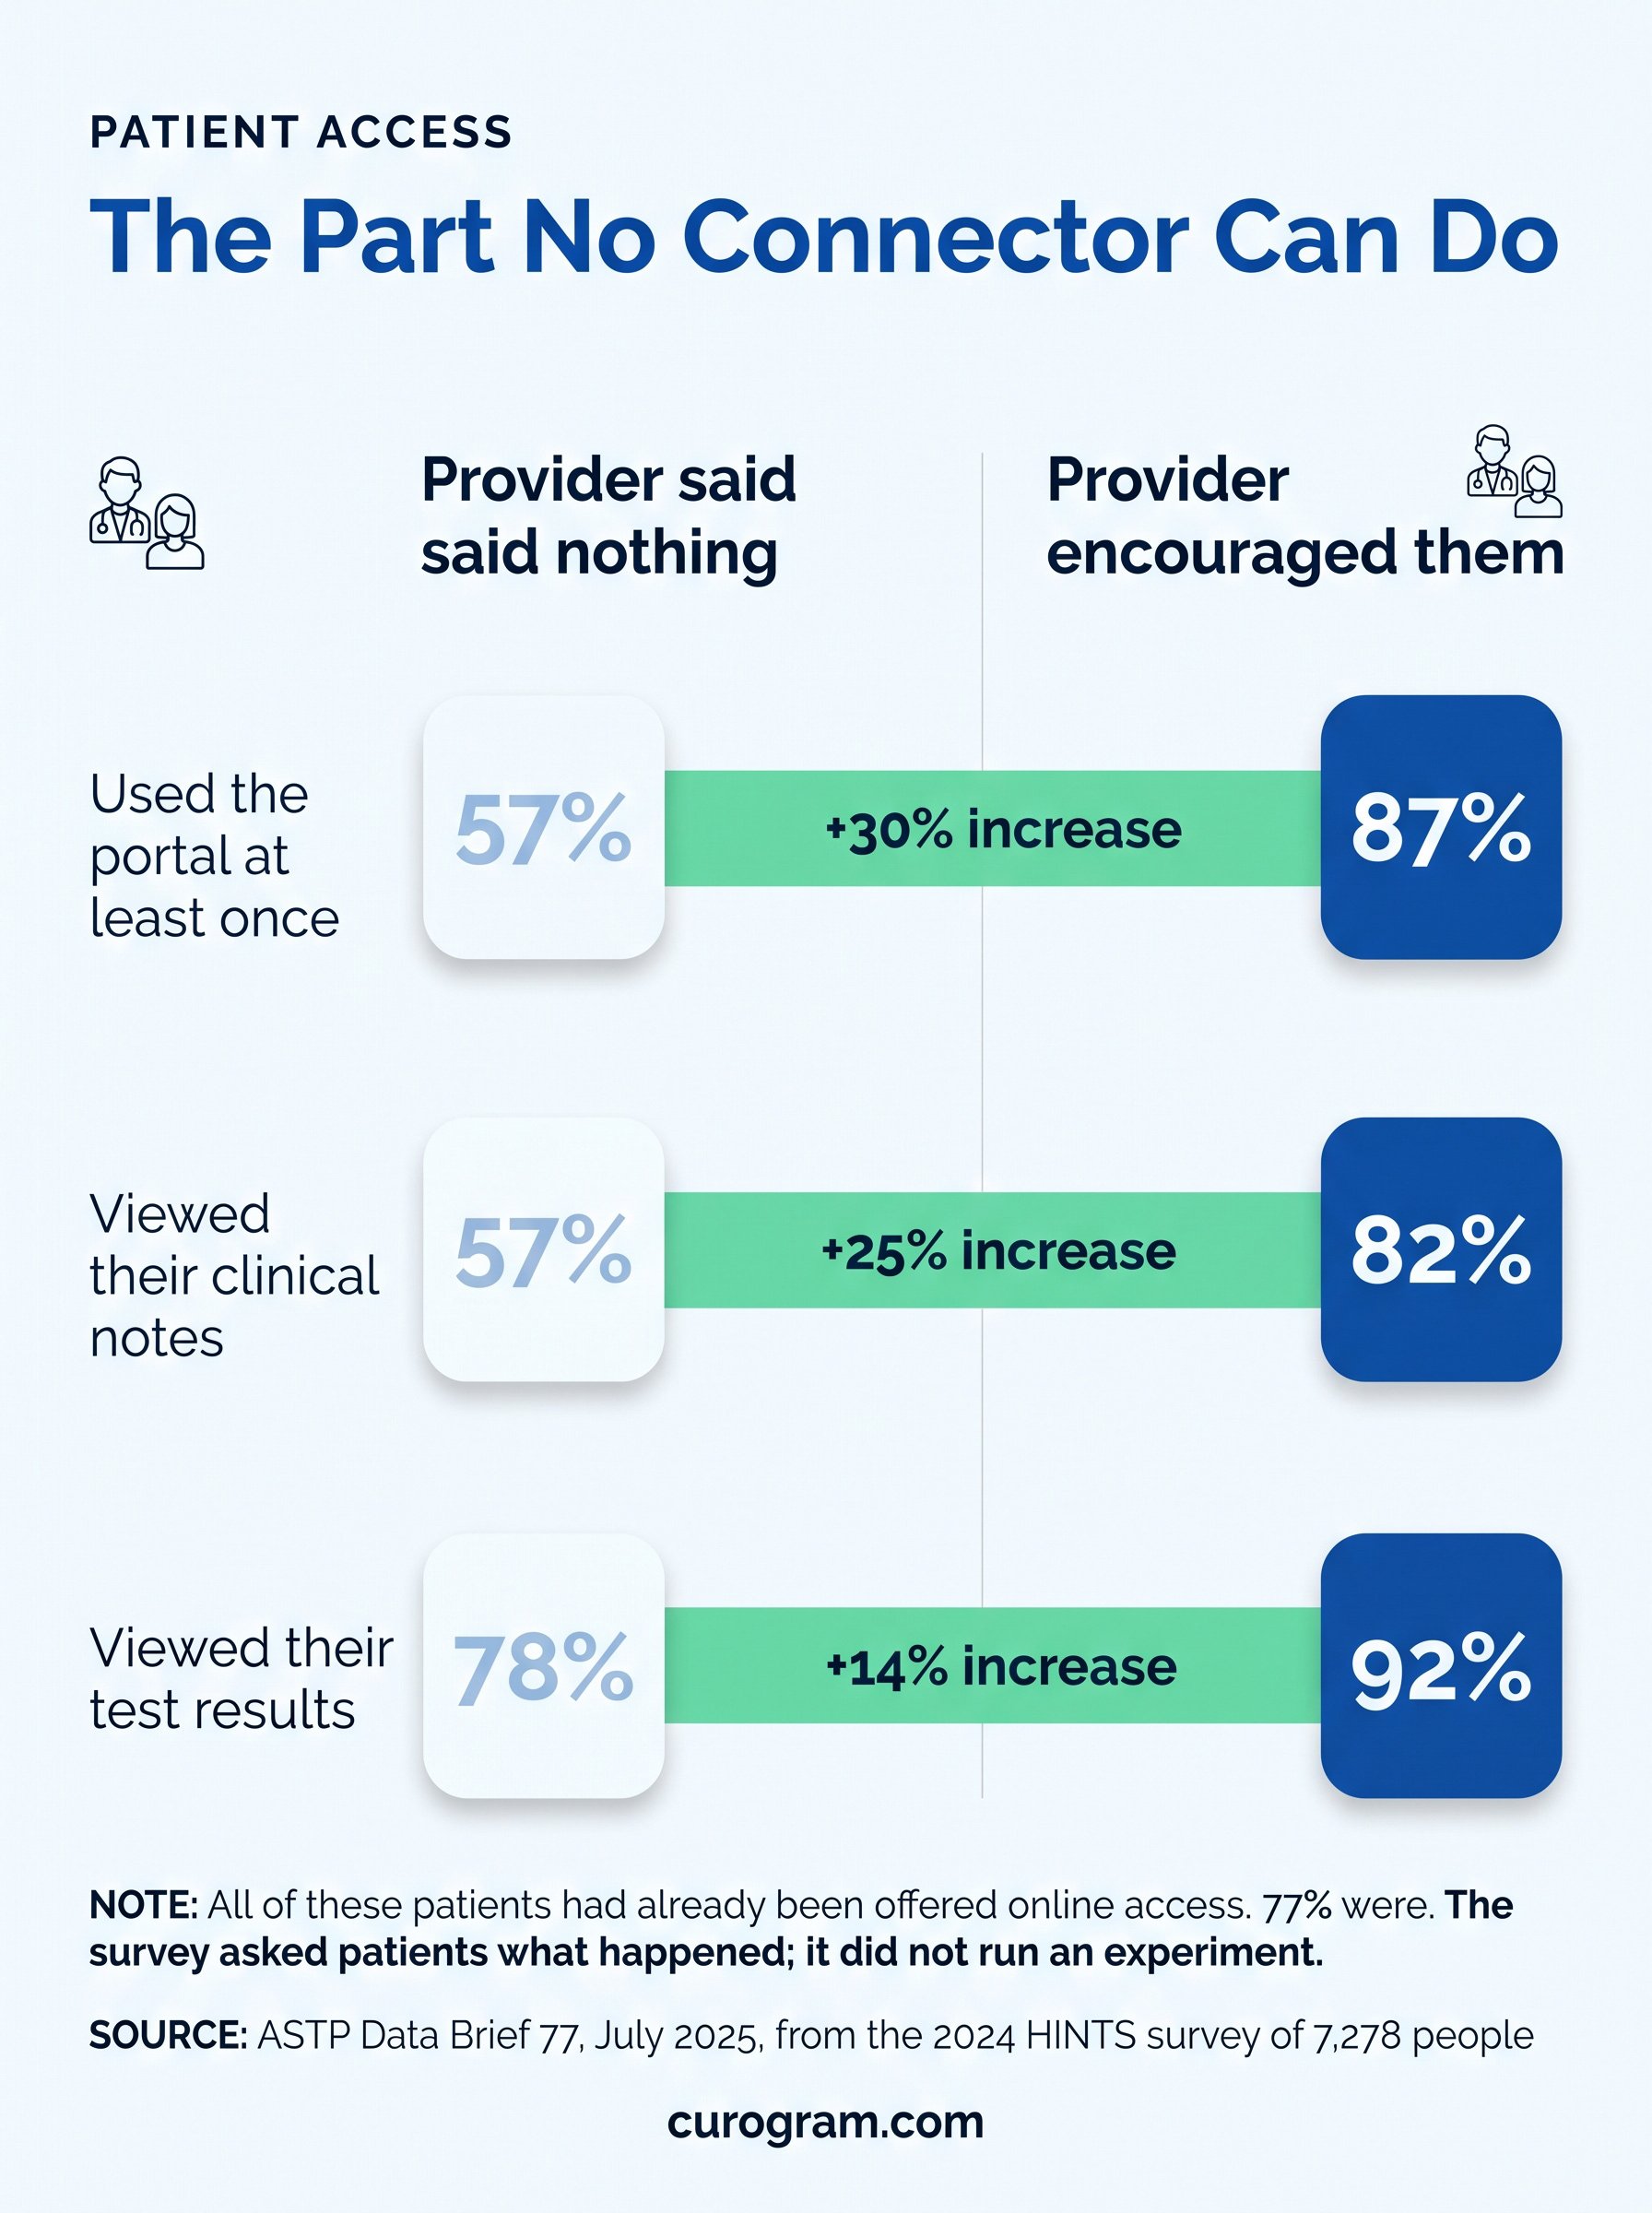
Tell patients to use it. A 2025 federal data brief drawn from a 2024 survey of 7,278 people puts a number on that.
77% were offered online access to their records. Among those whose provider encouraged them, 87% opened the patient portal. Among those not encouraged, 57% did.
A 30 point gap, closed by staff saying something at the desk. The gap for viewing clinical notes was wider still, at 82% against 57%. Which is the uncomfortable finding for anyone buying software. The connector is necessary, and it is not what moves the number.

Three things decide whether integration shows up in patient experience, and only one of them is technical. The connection has to run both ways. Reading the schedule is half a job, and the write-back is the half that saves anyone time.
The conduct has to be clean. Since July 2024, a referred information blocking finding reaches payment directly. Patients experience that same conduct as a missing record.
And somebody has to tell patients. That one costs nothing, moves the most, and appears in no implementation plan. Start with the schedule connection and one sentence at checkout. Measure your own no-show rate for a month before and a month after.
Book a Curogram demo and bring your own schedule to it. Ask to watch a form go out, come back, and land in the record with nobody retyping it.

EMR integration ROI sorted into three tiers: what you can count today, what needs a baseline first, and what is real but will never be a defensible...

Learn how integration with your EHR replaces confirmation calls, paper forms, and mailed statements with texts that sync, so your front desk works...

5 integration wins every clinic administrator will love. Learn how the EMR integration benefits for administrators bodes well for your medical...