
12 Key Pillars of Expert Radiology Medical Billing Service
Unlock efficiency and boost revenue in your practice with our definitive guide to radiology billing services and radiology billing and coding.
12 min read

Two clinics see the same patient on the same Tuesday. Clinic A checks her insurance when she reaches the front desk. Her plan changed in January. The line stalls while someone calls the payer, and she leaves upset about a bill she didn’t expect.
Clinic B ran that check 48 hours earlier. When it failed, she got a text asking for her new card. She sent a photo, saw her estimate, and paid her co-pay from a link before she left home.
The gap between those two visits is one step, done two days sooner and handled by a text. Revenue cycle management works this way at every stage.
Registration, eligibility, coding, charges, claims, billing, and collections each have a best time and a clear owner. Build your workflow for clinics around those times and let software carry the handoffs. You’ll see fewer denials and fewer days in A/R.
If parts of your cycle still run by hand, you know the signs. Claim status gets checked by phone. Follow-ups live on sticky notes, and your biller types the same notes into two systems. One missed step slows your cash, burns staff hours, and leaves patients unsure of what they owe.
This guide maps the six stages of the cycle, where each one tends to break, and the rule that fixes it. You’ll get a checklist that sets when eligibility, claim scrubs, statements, and follow-ups should happen.
A denial that lands weeks after a visit rarely starts in billing. Most trace back to an insurance card scanned wrong at check-in or a chart signed late. This section maps how money moves through your clinic, so each person on your team knows what their step feeds next.
Effective revenue cycle management relies on one set of steps that your whole team follows. A clear workflow for clinics covers every task from the first phone call to the final payment. It runs through six linked stages:
Each stage hands its data to the next one. Say a front desk staffer types one wrong digit in a member ID. That error rides along through coding and charge entry without anyone noticing. It surfaces weeks later as a denied claim, and your biller has to trace it back to check-in.
Each stage has a few habits that stop bad data from moving forward.
| Stage | What to Do | What It Prevents |
|---|---|---|
| Patient access | Collect correct demographics, insurance, and consent up front with digital forms. Run eligibility checks on their own. | Denials for coverage problems |
| Documentation and coding | Use standard visit types and templates that prompt for required details. | Coding errors and claim edits |
| Charge capture | Pull charges straight from EMR encounters. Match them against visits every day. | Services done but never billed |
| Claims management | Scrub each claim for format, coverage, and modifiers before it goes out. Send it electronically and track rejections in one queue. | Rejections from avoidable errors |
| Patient billing | Send statements by text or email with a pay link. Tailor messages to the balance and the patient’s plan. | Slow or missed patient payments |
| Collections | Set clear steps: reminders, then a payment plan offer, then a final notice, each on a set timeline. | Balances that age out unpaid |
If you can fix only one row this quarter, start with patient access. Errors made there pass through all five stages after it.
RCM runs best when every claim follows the same path. Write down your standard steps. Then build them into your software as rules, templates, and work queues that fill on their own. A biller hired last month can then follow the same steps as one who’s been with you for 10 years.
Next, track a short list of numbers each week:
Bring these to a brief weekly revenue huddle. Look at the outliers, such as one payer whose denials jumped since last month. Give each fix an owner and a due date before the huddle ends.
You don’t need a full overhaul to see results. These four changes can go live within the month:
With these steps in place, your workflow for clinics becomes predictable. It also gets easier to audit and to grow as you add providers.
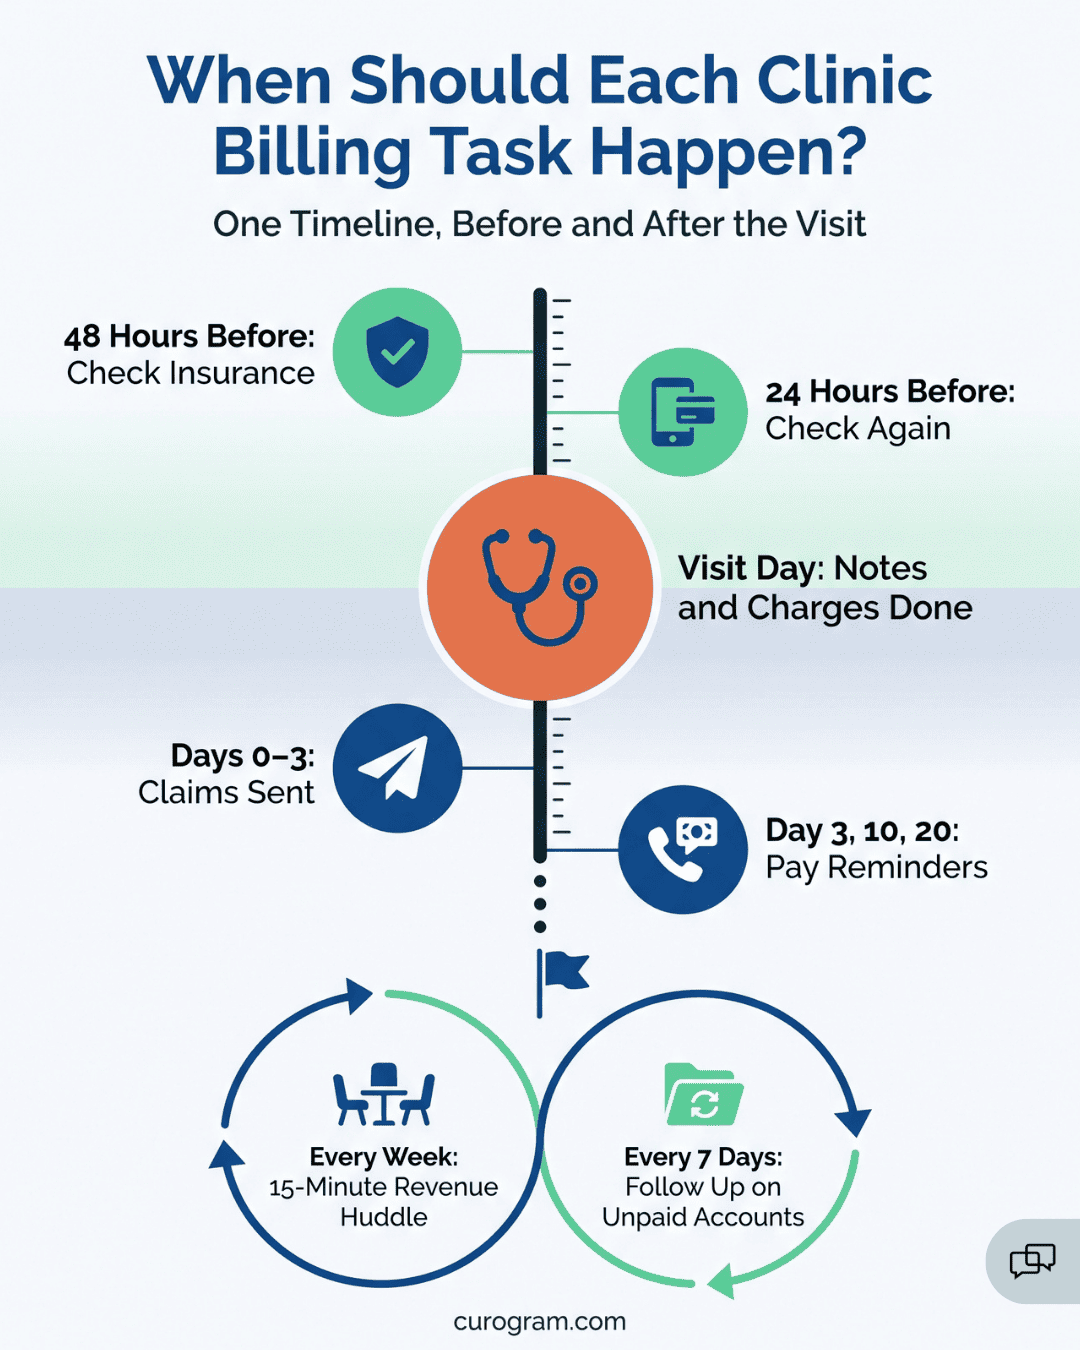
A bounced claim costs more than the money on it. Someone has to find it, fix it, send it again, and then wait another few weeks. Seven common breakdowns cause that rework, and each has a rule that stops it. None of the fixes needs new staff, only clear rules your software can follow.
Trouble often starts before the patient walks in. A patient switched plans in January, nobody ran eligibility again, and the visit turns out not to be covered. Now you have a denied claim and a patient holding a surprise bill.
Missing pieces in the chart cause the next round. A note without a signature, an order, or a diagnosis gets held for edits and rework. Charges leak out too. Someone keys them in by hand or misses an encounter, so the work gets done but never billed.
Denials tend to repeat. The same wrong modifier trips claim after claim, and so does a provider ID (NPI) mismatch or a Medicare local coverage rule (LCD). A claim scrubber could catch each one before it goes out.
Patient balances come in slowly when all you send is a paper statement. There’s no mobile option, the benefits aren’t clear, and no payment plan is offered. Your aging reports can’t sort by payer, reason, or staff owner, so worklists end up in spreadsheets.
Then there’s the toll on your team. Billers lose hours on hold with payers, only to hear a claim is still in process. Then they copy the same notes from one system to the next.
The fix is to automate handoffs and surface exceptions. Software moves routine work forward on its own, and only the problems land in front of a person. Start by matching each failure to one rule.
| Breakdown | Rule That Fixes It |
|---|---|
| Eligibility surprises | Check coverage 48 hours and again 24 hours before the visit. Send failures to a same-day worklist, and text the patient to upload a new insurance card. |
| Documentation gaps | Use EMR templates that won’t let a note close if a required item is missing for that visit type or payer. |
| Charge leakage | Build charges straight from orders and encounters. Run a daily “zero charge” report to find visits with nothing billed. |
| Repeat denials | Scrub claims with payer edits before sending. Resend fixed rejections on their own, and flag repeat denial codes so you can update templates. |
| Slow patient pay | Send digital statements with text-to-pay and offer automatic payment plans. Explain the explanation of benefits (EOB) in plain words. |
| Unclear A/R | Assign accounts to staff by payer and age. Set response times, such as touching each account every 7 days, and track them on a dashboard. |
Staff burnout has no single rule. It eases as the six rules above take status calls and copy-paste work off your team.
These fixes line up with the tools covered next. Those include revenue cycle management healthcare platforms, healthcare revenue cycle management automation, and payment flows patients find easy to use.
Roll them out one at a time, starting with the breakdown that costs you the most. Your denial report, sorted by reason, usually shows you which one that is.
Each item below is a rule or a setting, not a new system. You can turn them on one at a time.
Most front desk work can happen before the patient ever walks in. Set each step to fire on its own schedule.
| When | What Happens |
|---|---|
| At scheduling | The patient gets a secure link for demographics, consent forms, and insurance card photos. The form won’t send until required fields are filled. Eligibility runs for the first time. |
| Before the visit | Eligibility runs again. If coverage doesn’t match, the patient gets a text asking them to update their insurance. |
| Before the visit | The patient sees an estimate of what they’ll owe, plus a link to pay the co-pay ahead of time. |
A claim that pays on the first try never touches your rework queue. Three kinds of automation get you there.
Smart templates prompt clinicians for the details coders need: which side of the body, how many units, and how much time was spent. A knee injection note that doesn’t say left or right gets caught before it’s signed.
Scrubbing software checks each claim against that payer’s own edits before it goes out. These include modifiers and Medicare’s local and national coverage rules (LCDs and NCDs).
Electronic submission sends claims in batches. Rejections get worked on their own, and each one is tracked by payer and denial reason.
Text and email go out first, each with a link to pay from a phone. Paper is the backup, sent only when a patient doesn’t respond or asks for it.
EOBs are hard to read. Turn yours into one plain line, and link to a summary of the patient’s benefits. A sample message:
Your plan paid $140 for your March 4 visit. Your share is $35.
Let patients set up a payment plan themselves, right from the statement. With their consent, keep a card on file so plan payments run on schedule. Every plan a patient sets up alone is one less call to your billing line.
You’re already tracking the core numbers each week. These cuts show where the automation is working and where it isn’t.
| Number | Cut It This Way |
|---|---|
| Clean-claim rate and first-pass resolution | Track them side by side. A gap between them means claims go out clean but still don’t pay. |
| Denial rate | Look at the top five denial codes and the top five payers. |
| Days in A/R | Watch the current figure and its trend, plus the % of balances over 90 days. |
| Patient payments | Track time-to-pay and how many statements each account needs before it’s paid. |
These automations run without a person starting each step. That lets your revenue cycle management healthcare program take on more visits without adding staff.

High-deductible health plans push more of each bill onto the patient. When the only way to pay is a paper statement or a phone call during office hours, balances sit.
Your staff end up spending afternoons dialing patients who don’t pick up. Healthcare revenue cycle management works better when the bill lands on the patient’s phone.
Text-to-Pay sends a secure payment link by text for co-pays, deposits, and balances after the visit. Patients pay from any device in seconds, with no login and no call to your office.
Reminders run on a schedule you set, such as day 3, day 10, and day 20. They stop the moment a patient pays. If a balance is still open, the next one can offer a payment plan.
Itemized statements and explanation of benefits (EOB) summaries go out through HIPAA-compliant messaging. Patients can see what they owe and why.
Your team can also pair payments with Curogram’s 2‑way texting, appointment reminders, and online forms in one place. When a patient replies, “Can I split this into two payments?”, your biller answers in the same thread. No callback is needed.
| When | What Happens |
|---|---|
| Before the visit | Eligibility confirms coverage, and an estimate is created. |
| Before arrival | The patient gets a text with a co-pay link and pays ahead. |
| After the payer processes the claim | A balance text goes out with the statement and EOB summary. |
| If it’s still unpaid | Automated reminders offer a payment plan. Your staff get an alert only for exceptions. |
Patient payments come in faster, and fewer billing calls ring into your office. Every message and payment leaves an audit trail, and the whole flow stays HIPAA compliant. Curogram works alongside your practice management system and EMR, so your core systems stay in place.
A structured workflow for clinics gives each billing task a set time and a set owner. That keeps money from slipping out between steps.
Miss one eligibility check, and you can end up with a denied claim and a patient balance no one can collect. Skip the daily charge match, and a whole visit can go unbilled.
Pair the checklist below with automation, and your software takes over the repeat work. Eligibility tools, claim scrubbers, and digital billing run those steps on their own, leaving your staff free for exceptions and patients.
Built-in reports show patterns, too. A spike in denials from one payer stands out within days, so you can fix the cause before it spreads.
Most of the money a clinic loses never shows up as one big write-off. It slips out in small pieces: a plan change nobody caught, a visit with no charge attached, a $40 balance on a paper statement sitting in a kitchen drawer.
That’s why we’d start at the front desk. An error made at check-in rides through every stage after it, and it’s cheapest to fix right where it starts.
With clear workflows for clinics in place, each handoff has a set time and a named owner. Problems surface the same day instead of weeks later as a denial.
Automation then takes the repeat steps off your team’s desk. Eligibility runs on its own, claims get scrubbed before they leave, and patients pay from a text.
Curogram handles the patient side of that work. HIPAA-compliant messaging, digital forms, reminders, and Text-to-Pay all run from one platform that works alongside your EMR. Balances get paid without a phone call, so your staff can focus on the patients in the room.
Stop running 42 CFR Part 2 risk through staff personal phones and sticky notes. Schedule a demo to see how Curogram's HIPAA- and Part 2-aware texting locks down every patient message.

Unlock efficiency and boost revenue in your practice with our definitive guide to radiology billing services and radiology billing and coding.

Learn 11 medical billing tips that reduce claim denials at the source, protect your practice revenue, and help you collect faster on every patient...

 Mira Gwehn Revilla : 2/1/26, 8:00 AM
Discover the cost benefits of a paperless medical office. Learn how Curogram’s digital patient forms reduce overhead and increase practice revenue.