
1 min read
Which Part of Your Workflow Needs Integration First?
💡Not every process needs integration on day one. The key is knowing where to begin. By identifying the most painful parts of your...
6 min read

Healthcare workflow bottlenecks show up as daily friction: tasks take longer than they should, calls stack up, and staff spend more time moving information than caring for people. Those are symptoms. Only one of them is the constraint.
AMN Healthcare surveyed 1,391 physician offices across 15 metro areas in 2025 and found new patients waiting 31 days on average, up from 26 in 2022. Orthopedic surgery went the other way, dropping 29% to 12 days.
One specialty moved its slowest step while the rest automated around theirs. That gap is what this article is about: how to tell which of your handoffs is actually holding the others back, and why fixing the wrong one costs a year.
A bottleneck caps everything downstream of it. Speed up any other step, and you have not gained a minute, because work still queues at the same place.
The phone rings where everyone can hear it, so it gets fixed first. Meanwhile, a stack of returned intake forms waits two days to be keyed, and nobody hears a form. Clinics reliably know their call volume and reliably cannot state their form turnaround.
MGMA asked 294 practice leaders in March 2026 where phone time actually goes. Eligibility and prior authorization took 45%, scheduling 31%, intake 9%, refills 6%. That is how the phone hour gets spent, which is a volume number rather than a wait.
Add online booking to a schedule that is already 31 days out, and you have not improved access. You have filled the queue faster and given more patients a longer wait to be annoyed about.
Tools land; work does not move. In September 2025, 68% of medical groups reported adding or expanding AI tools. By June 2026, a separate MGMA poll found 68% had not redesigned a role or adjusted staffing to match.
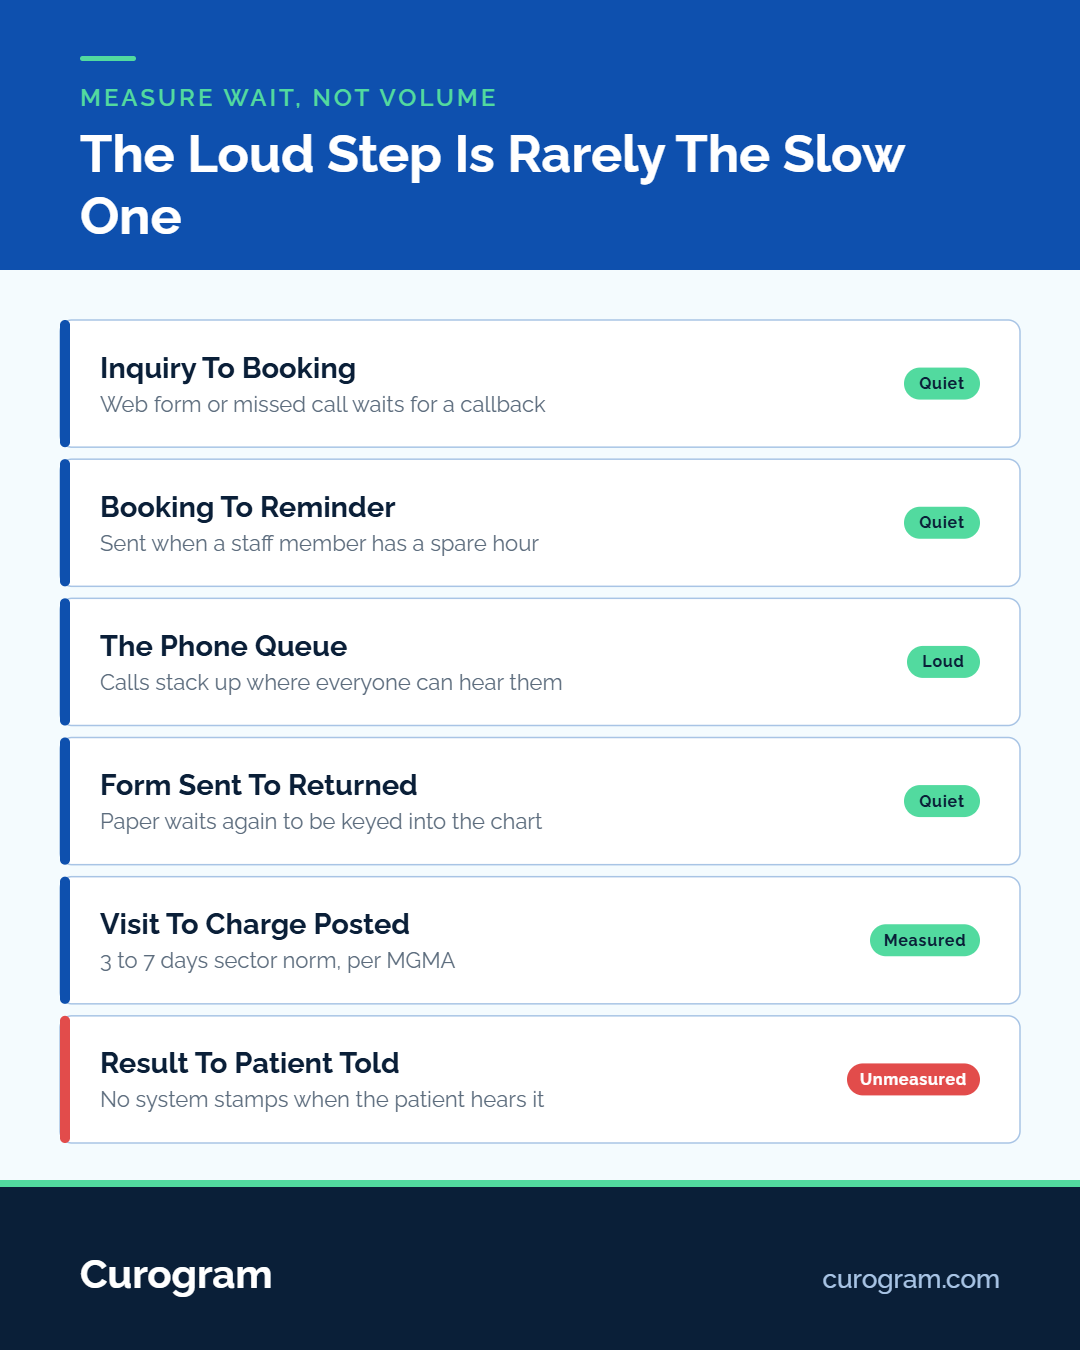 Six Handoffs Where Work Sits Waiting
Common EMR workflow issues cluster at the seams between systems, where data changes hands. Six seams cover most clinics.
If a reminder is composed by a person, it goes out when someone has a spare hour. If intake forms are mailed or handed over on paper, the wait is however long until a staff member types them in. Both gaps are invisible until timed.
MGMA puts the sector lag between visit and submitted claim at three to seven days. The results handoff has no benchmark at all, which is usually a sign nobody measures it, and it carries the highest clinical stakes of the six.
A website form or missed call that waits until the afternoon callback has already lost most patients. This seam produces no complaints from staff, because the people affected by it never became patients.
The sixth seam draws no complaints at all, because the patient stopped coming and nobody is waiting on you. A recall date passes, the list grows, and the gap gets measured in months rather than days.
Broadcast messaging closes this one at list scale, which is the only practical route once the backlog runs to hundreds of names.
Pick five patients and follow each one through. You are timing gaps between steps, not the steps themselves, and one week of real cases beats any dashboard.
For each of the five patients, write the timestamp at both ends of every handoff. That means booking to reminder sent, form sent to form returned, visit end to charge posted, and result received to patient told.
Use dates and times already in the chart wherever you can. Ask staff only for the gaps the system does not record, since those are usually the longest ones.
|
Handoff |
What to time |
Watch for |
|---|---|---|
|
Booking to reminder |
Appointment created until first reminder sent |
Anything over 24 hours means a person composes it |
|
Form sent to returned |
Link sent until data lands in the chart |
Paper adds a second wait for keying |
|
Inquiry to booking |
Web form or missed call until slot held |
Same-day is the threshold most patients apply |
|
Visit to charge posted |
Encounter closed until claim submitted |
Three to seven days is the sector norm, per MGMA |
|
Result to patient told |
Result received until the patient hears it |
Usually the longest gap and the least measured |
|
Overdue to rebooked |
Recall date passed until the patient books |
Months, not days. Nobody chases you on this one |
Time each gap for five patients. The widest one is your constraint.
The widest gap wins, even when it is not the one staff complain about. That mismatch is the normal outcome, not a sign you measured wrong.
An illustrative version of how it lands: booking to reminder comes back at 6 hours, forms at 2 days, results at 9 days. The team had spent the quarter asking for a better phone system. The phone did not place in the top three.

Healthcare workflow automation earns its keep at one seam at a time. Take the widest gap, remove the manual step inside it, and leave every other seam alone for a month. Deciding which part of your workflow to integrate first is the same question asked once, with data.
Most gaps close when the trigger changes from a spare hour to an event. Reminders fire from the appointment record. Forms send when the booking is confirmed. Payment links go out when the balance posts.
Patient notifications that read from the schedule take the person out of the trigger entirely, which is what keeps a closed gap closed instead of dependent on a quiet week.
Routine phone traffic moves to text so staff work several threads at once, and each exchange logs against the right chart rather than a sticky note.
A form that syncs into the chart closes the keying wait and the typing error in one move. CAQH estimates fully electronic administrative workflows save about 70 minutes per patient visit across the industry.
Patient intake is the usual first pick. The gap is wide, the trigger is a date, and no judgment call sits inside it.
Not every wide gap should be handed to software. In a February 2026 MGMA poll, prior authorization drew just 16% of practices' automation plans. That restraint makes sense. Hard cases need someone who can argue with a payer.
Automate the status chasing around those steps and leave the decision with a person. The same rule applies to abnormal results, where the routing can be automatic and the call cannot.
One name at a time will never clear a recall backlog. Mass text messaging sends the whole list on a schedule, and the staff job turns into reviewing replies rather than dialing.
Behavioral health and addiction treatment programs carry the hardest version of this. Alumni engagement after discharge has real clinical weight and almost never has a date attached to it.
Close the widest gap, and a different seam becomes the slowest. This is expected. Re-time the same six handoffs 30 days later and work the new leader.
Two things usually surface on the second pass. A gap you closed has drifted back because someone muted a notification. And a seam that looked fine at five patients looks worse at twenty, which is the point at which administrative delays stop being anecdotes.
Curogram is not an EMR and does not replace one. It runs the patient-facing seams from the table above, which are the ones where a person is usually the trigger.
Secure Online Patient Forms are sent on booking and write answers into the chart, closing the keying wait. Patient Reminders fire from appointment data rather than a spare hour. Two-Way HIPAA-Compliant Texting turns the phone queue into threads, and Text-to-Pay closes the balance seam with a link instead of a third statement.
All of it reads from your current system through Curogram's EMR integration, and the platform is HIPAA compliant and SOC 2 Type II certified. Charting and billing stay where they are.
Five patients and a week of timestamps will tell you more than a year of dashboards. Most clinics find the widest gap somewhere nobody was complaining, which is exactly why it stayed wide.
Clinic workflow automation works when it is pointed at that gap. Pointed anywhere else, it produces a faster queue for the same wait.
Schedule a demo and bring your timed handoffs. We will show you which seams Curogram closes inside your current EMR, and which ones need a scheduling change instead.

1 min read
💡Not every process needs integration on day one. The key is knowing where to begin. By identifying the most painful parts of your...

1 min read
💡Clinic workflow integration changes everything. Before integration, staff juggle phone calls, paperwork, and disconnected systems. After...

1 min read
💡 A small clinic fixed its biggest workflow bottlenecks by integrating communication with its EMR. Before: Staff spent hours on phones, patients...