
 Carylee Gali
Louisiana Telemedicine: Laws, Licensing, and Reimbursement in 2026
 Michael Hsu : 6/6/20, 8:36 AM
The provider's ultimate guide to telemedicine in Louisiana. Learn how to streamline your telehealth business and keep ahead of the competition.

The mechanics of a video visit stopped being interesting around 2021. A patient taps a link and joins from a phone. What changed is everything around the visit. Coverage, prescribing authority and the dates attached to both.
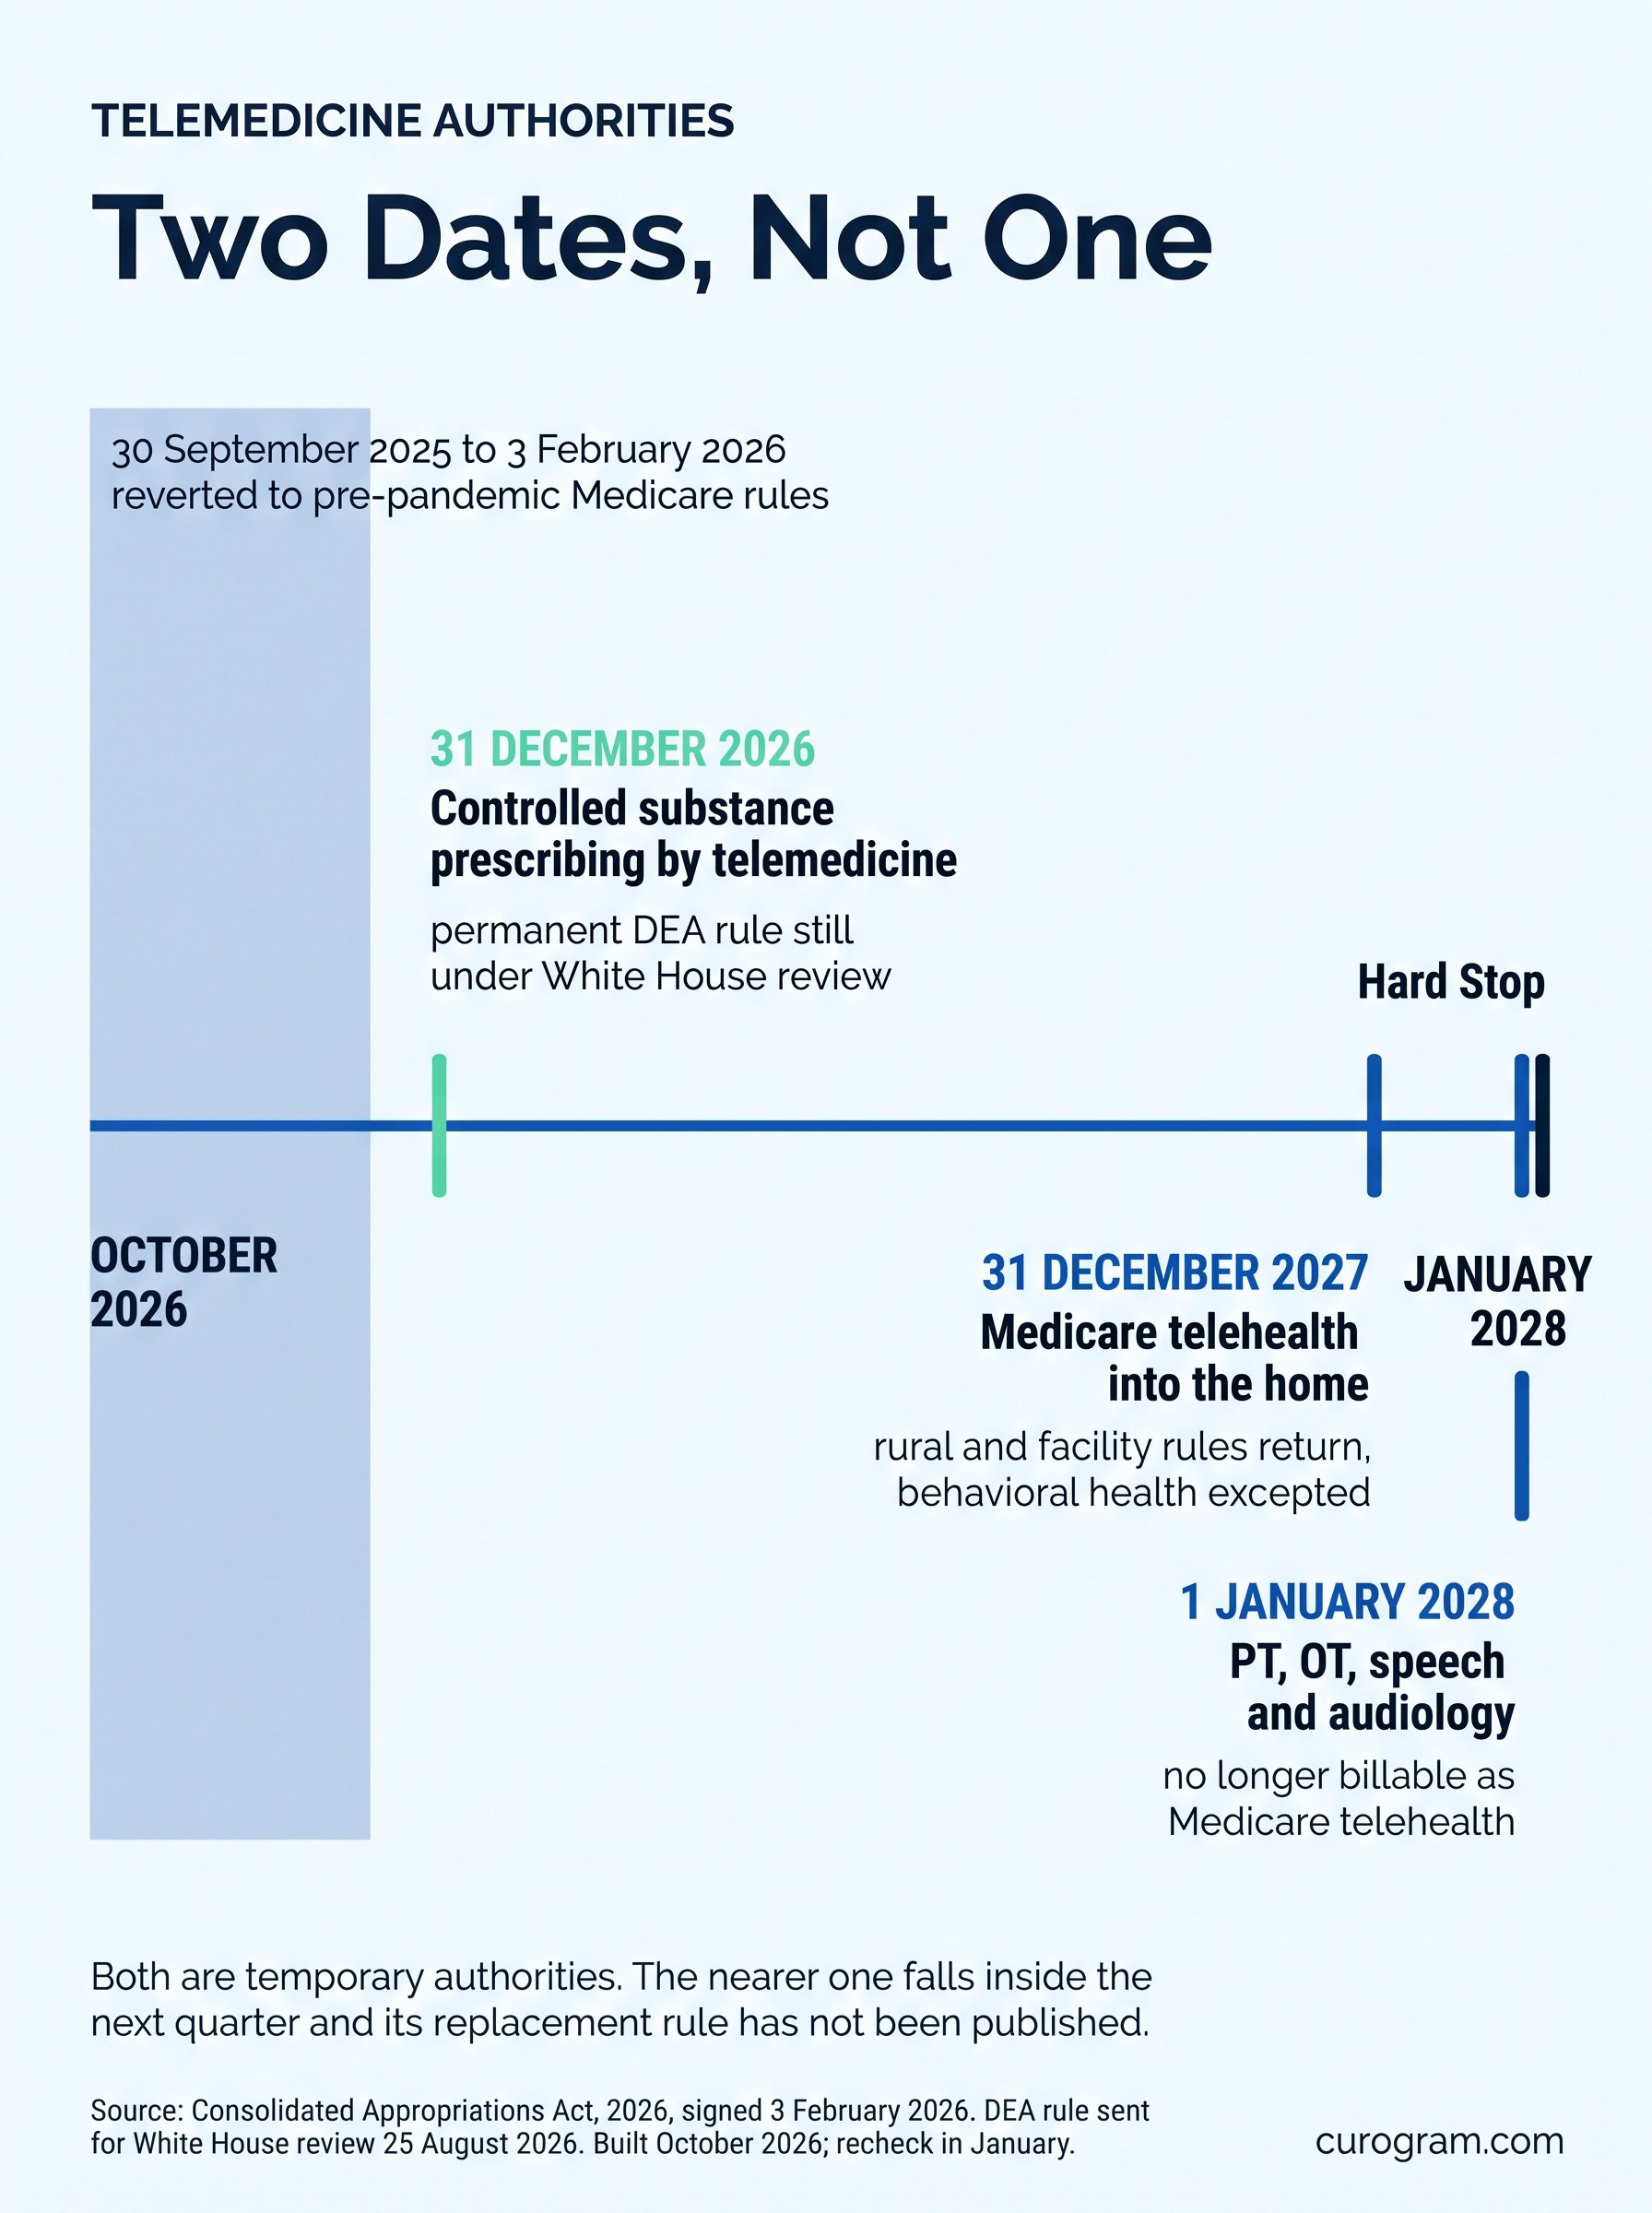
Medicare pays for telehealth into the home through December 31, 2027. That is a real date, not a permanent arrangement.
The same coverage already lapsed once. It expired on September 30, 2025 and was not restored until February 3, 2026. A nearer deadline sits on prescribing. Controlled substance prescribing by telemedicine runs through December 31, 2026.
So the honest answer covers the visit and the calendar. Below: both, plus what a practice has to have in place. Both dates are temporary authorities. Neither is law settled for good.
Yes, and that question is settled enough that it is no longer the useful one. Payers, state boards and Medicare all treat it as care.
The live question is narrower. Which services, for which patients, in which place, and until when.
A Medicare patient can be at home, anywhere in the country, through the end of 2027. The Consolidated Appropriations Act, 2026 set that date when it was signed on February 3, 2026.
From January 1, 2028, the old rules return unless Congress acts again. Most patients would need to be in a rural area at a medical facility.
Behavioral health is the exception and keeps home as an originating site. Everything else goes back.
Nothing about the visit itself changes on those dates. What changes is whether anyone pays for it.
Four dates worth putting in a diary rather than trusting to memory.
|
Flexibility |
Runs until |
What happens next |
|---|---|---|
|
Controlled substance prescribing by telemedicine |
Dec 31, 2026 |
Permanent DEA rule still under White House review |
|
Medicare telehealth into the patient's home |
Dec 31, 2027 |
Rural and facility rules return, except behavioral health |
|
Physical and occupational therapy, speech, audiology |
Dec 31, 2027 |
No longer billable as Medicare telehealth |
|
Behavioral health in-person visit requirement |
Waived to Dec 31, 2027 |
In-person within six months, then every 12 months |
Coverage expired on September 30, 2025. From October 1, Medicare telehealth reverted to the pre-pandemic rules.
Restoration came on February 3, 2026. Practices that had built a care model on the flexibilities spent four months improvising.
That history is the reason to treat 2027 as a planning assumption rather than a settled fact.
 Telemedicine and telehealth refer to different scopes of healthcare.
Telehealth is the wider word. It covers remote clinical care plus education, training and administration. Telemedicine is the clinical core of it. Remote examination, diagnosis and treatment of a patient.
The distinction earns its keep at billing. Payer policies and state rules are written against one term or the other. Pick the wrong one and you land on the wrong rule. Check which word your own payer contracts use before assuming a policy applies.
Most people use the two words as one. That is fine in conversation and costly on a claim form. Your EHR may use a third label again. Check what it calls the visit type before anyone bills it.
The split shapes consent too. A teaching session and a diagnosis do not need the same paperwork. State law adds a third layer on top. Some states define telemedicine narrowly enough to exclude audio-only calls.
Four modalities cover almost everything a practice will do remotely. Each has its own billing and consent behavior.
Most practices start with live video and add one more. Running all four at once is a procurement decision rather than a clinical one.
Coverage follows the modality, not the diagnosis. The same condition can be payable by live video and not by store-and-forward.
Ask your payer which of the four they pay for by name. A yes to telehealth is not a yes to all four.
Remote monitoring is the one practices underestimate. It needs devices shipped, patients onboarded and somebody watching the readings.
A visit runs in six steps. Book it, send the link, confirm identity, consult, prescribe or refer, then document. Step three gets skipped more than any other. Ask for a date of birth before clinical talk starts.
Step two is where most visits are lost. We covered video visits with no app download on Oracle Health, because an install screen is where older patients stop.
Staff side matters as much. Our writeup on one-click video visit launch in Practice Fusion covers starting a visit without leaving the schedule.
Patients need preparation too. We walked through how to prepare for a telehealth visit in athenahealth. Most of it is testing audio before the clock starts.
The video stream is rarely the problem. Consumer meeting tools without a signed agreement are, and so is clinical detail typed into an ordinary text message.
On penalties, this page used to quote $100 to $50,000 per violation. Those are the base figures in section 160.404.
The same section says those amounts are adjusted every year and published separately. Quote the adjusted table rather than the base one.
Send a link rather than the detail itself. A wrong number then gets a link it cannot open.
Document the visit the way you would in person. The note is the record, whatever the room looked like.
A solo practice may need nothing more than compliant two-way video. A group with several sites needs the schedule, the waiting room and the record to agree.
Ask what the platform writes back to the chart. A visit that leaves no trace there leaves documentation to somebody that evening.
Ask about the patient side separately. No download, no account, and a link that works on an old phone is most of the adoption problem solved.
Train the front desk on the join rather than the clinical part. They are the ones who talk a patient through it.
Encryption in transit and at rest, role-based access, and audit logs are the baseline. A business associate agreement should come as standard rather than as an upgrade.
No vendor can make a practice compliant on its own. Compliance is shared, and the written risk assessment stays with the practice.
Ask who tests the platform after an EHR upgrade. A video link that breaks between releases costs a full clinic session.
That framing matters because an earlier version of this page claimed patient data was 100% secure. No platform can promise that, and the sentence is gone.

Curogram HighlightCurogram's Telehealth Software opens in a browser, so patients join from a text link with nothing to install. Staff run the waiting room from the same inbox they already use for reminders and replies. A business associate agreement is standard. The visit attaches to the patient record rather than sitting in a separate tool. |
Prescribing is the near one. Controlled substance prescribing by telemedicine runs through December 31, 2026. DEA sent its permanent rule for White House review on August 25, 2026.
That rule has not been published. Practices that prescribe this way should be checking weekly rather than planning around the draft.
State rules sit on top of the federal ones and do not move together. Check your own board before assuming the federal date is the only one.
Then put December 2027 in the calendar for the Medicare side. Coverage that already lapsed once can lapse again.
Write down who checks these dates and how often. A deadline nobody owns is a deadline that passes.
None of this is legal advice, and your own compliance lead should see whatever you decide.
Check that your malpractice cover reaches remote visits in every state you see patients. Carriers vary, and it is a short phone call.
Book a Curogram demo. One pass covers the patient link, the waiting room and the write-back to the chart.
 Michael Hsu : 6/6/20, 8:36 AM
The provider's ultimate guide to telemedicine in Louisiana. Learn how to streamline your telehealth business and keep ahead of the competition.
 Michael Hsu : 6/19/20, 10:40 AM
Looking to capture the telehealth market? Here are the best methods that will help you practice telemedicine in Virginia profitably and successfully.

 Jo Galvez : 4/12/26, 9:00 AM
Discover how Curogram enhances telemedicine with HIPAA-compliant communication, appointment reminders, and integrated patient engagement features.