
 Michael Hsu
Telemedicine Virginia: A Comprehensive Guide
 Michael Hsu : 6/19/20, 10:40 AM
Looking to capture the telehealth market? Here are the best methods that will help you practice telemedicine in Virginia profitably and successfully.

A family doctor in Boone has a patient who moved to Johnson City for work. Same region, 45 minutes apart, two states.
Until recently, that was a licensing problem with no quick answer. As of January 2026, it has one. North Carolina changed more telemedicine rules in the last two years than in the decade before it.
Our position: the state is no longer the laggard it was on access. On payment, it has not moved at all. What follows: what the board expects, what Medicaid now pays, and the gap that has not moved since 2015.
North Carolina has 100 counties and a geography that makes some of them hard to serve.
The two words get used as if they were one, and the line between them is thin. Telemedicine tends to mean care at a distance. Telehealth covers that plus teaching, admin, and remote checks.
NC Medicaid settled the question in practice. Its policy covers both under one roof, so the label matters less than the billing code. Where it helps most is the drive. A mountain county patient and a coastal one both lose a half day to a 15-minute follow-up.
The North Carolina Medical Board's telemedicine position statement, amended in March 2024, sets the expectation. A virtual visit is judged the way an office visit is.
No in-person meeting is required first. A real-time video visit can establish the relationship.
Audio-only calls, texts, emails, and online questionnaires on their own do not. The board treats those as supplements rather than a starting point.
Staff time is the hidden cost of virtual care, and it lands on the front desk. Practices measuring telehealth workflow efficiency in Elation Health find most of it goes to getting patients connected. Train for the join, not the platform. The question a patient asks is never about video quality.
The evaluation has to support the diagnosis, the same as in person. If the exam needs hands or a device, the visit needs to move.
Document what you could and could not assess. Groups running telehealth in GE Centricity write the visit back to the chart so that the record exists without retyping.
The board holds prescribing to the in-person standard. It is strictest on controlled substances for pain.
NC runs a Controlled Substances Reporting System that prescribers are required to use. Check it before writing, and check the federal rules separately, since those move on their own schedule.
A telemedicine encounter needs the same record an office visit gets. The board expects the full exchange documented, including email, text, and photos.
Consent belongs in that record. The board asks for informed consent documents covering the risks, limits, alternatives, and benefits. Keep the thread with the chart rather than in a staff inbox. A record an auditor cannot find is a record you do not have.
This is the rule that changed. A visit happens where the patient is, so treating a North Carolinian has always required NC licensure.
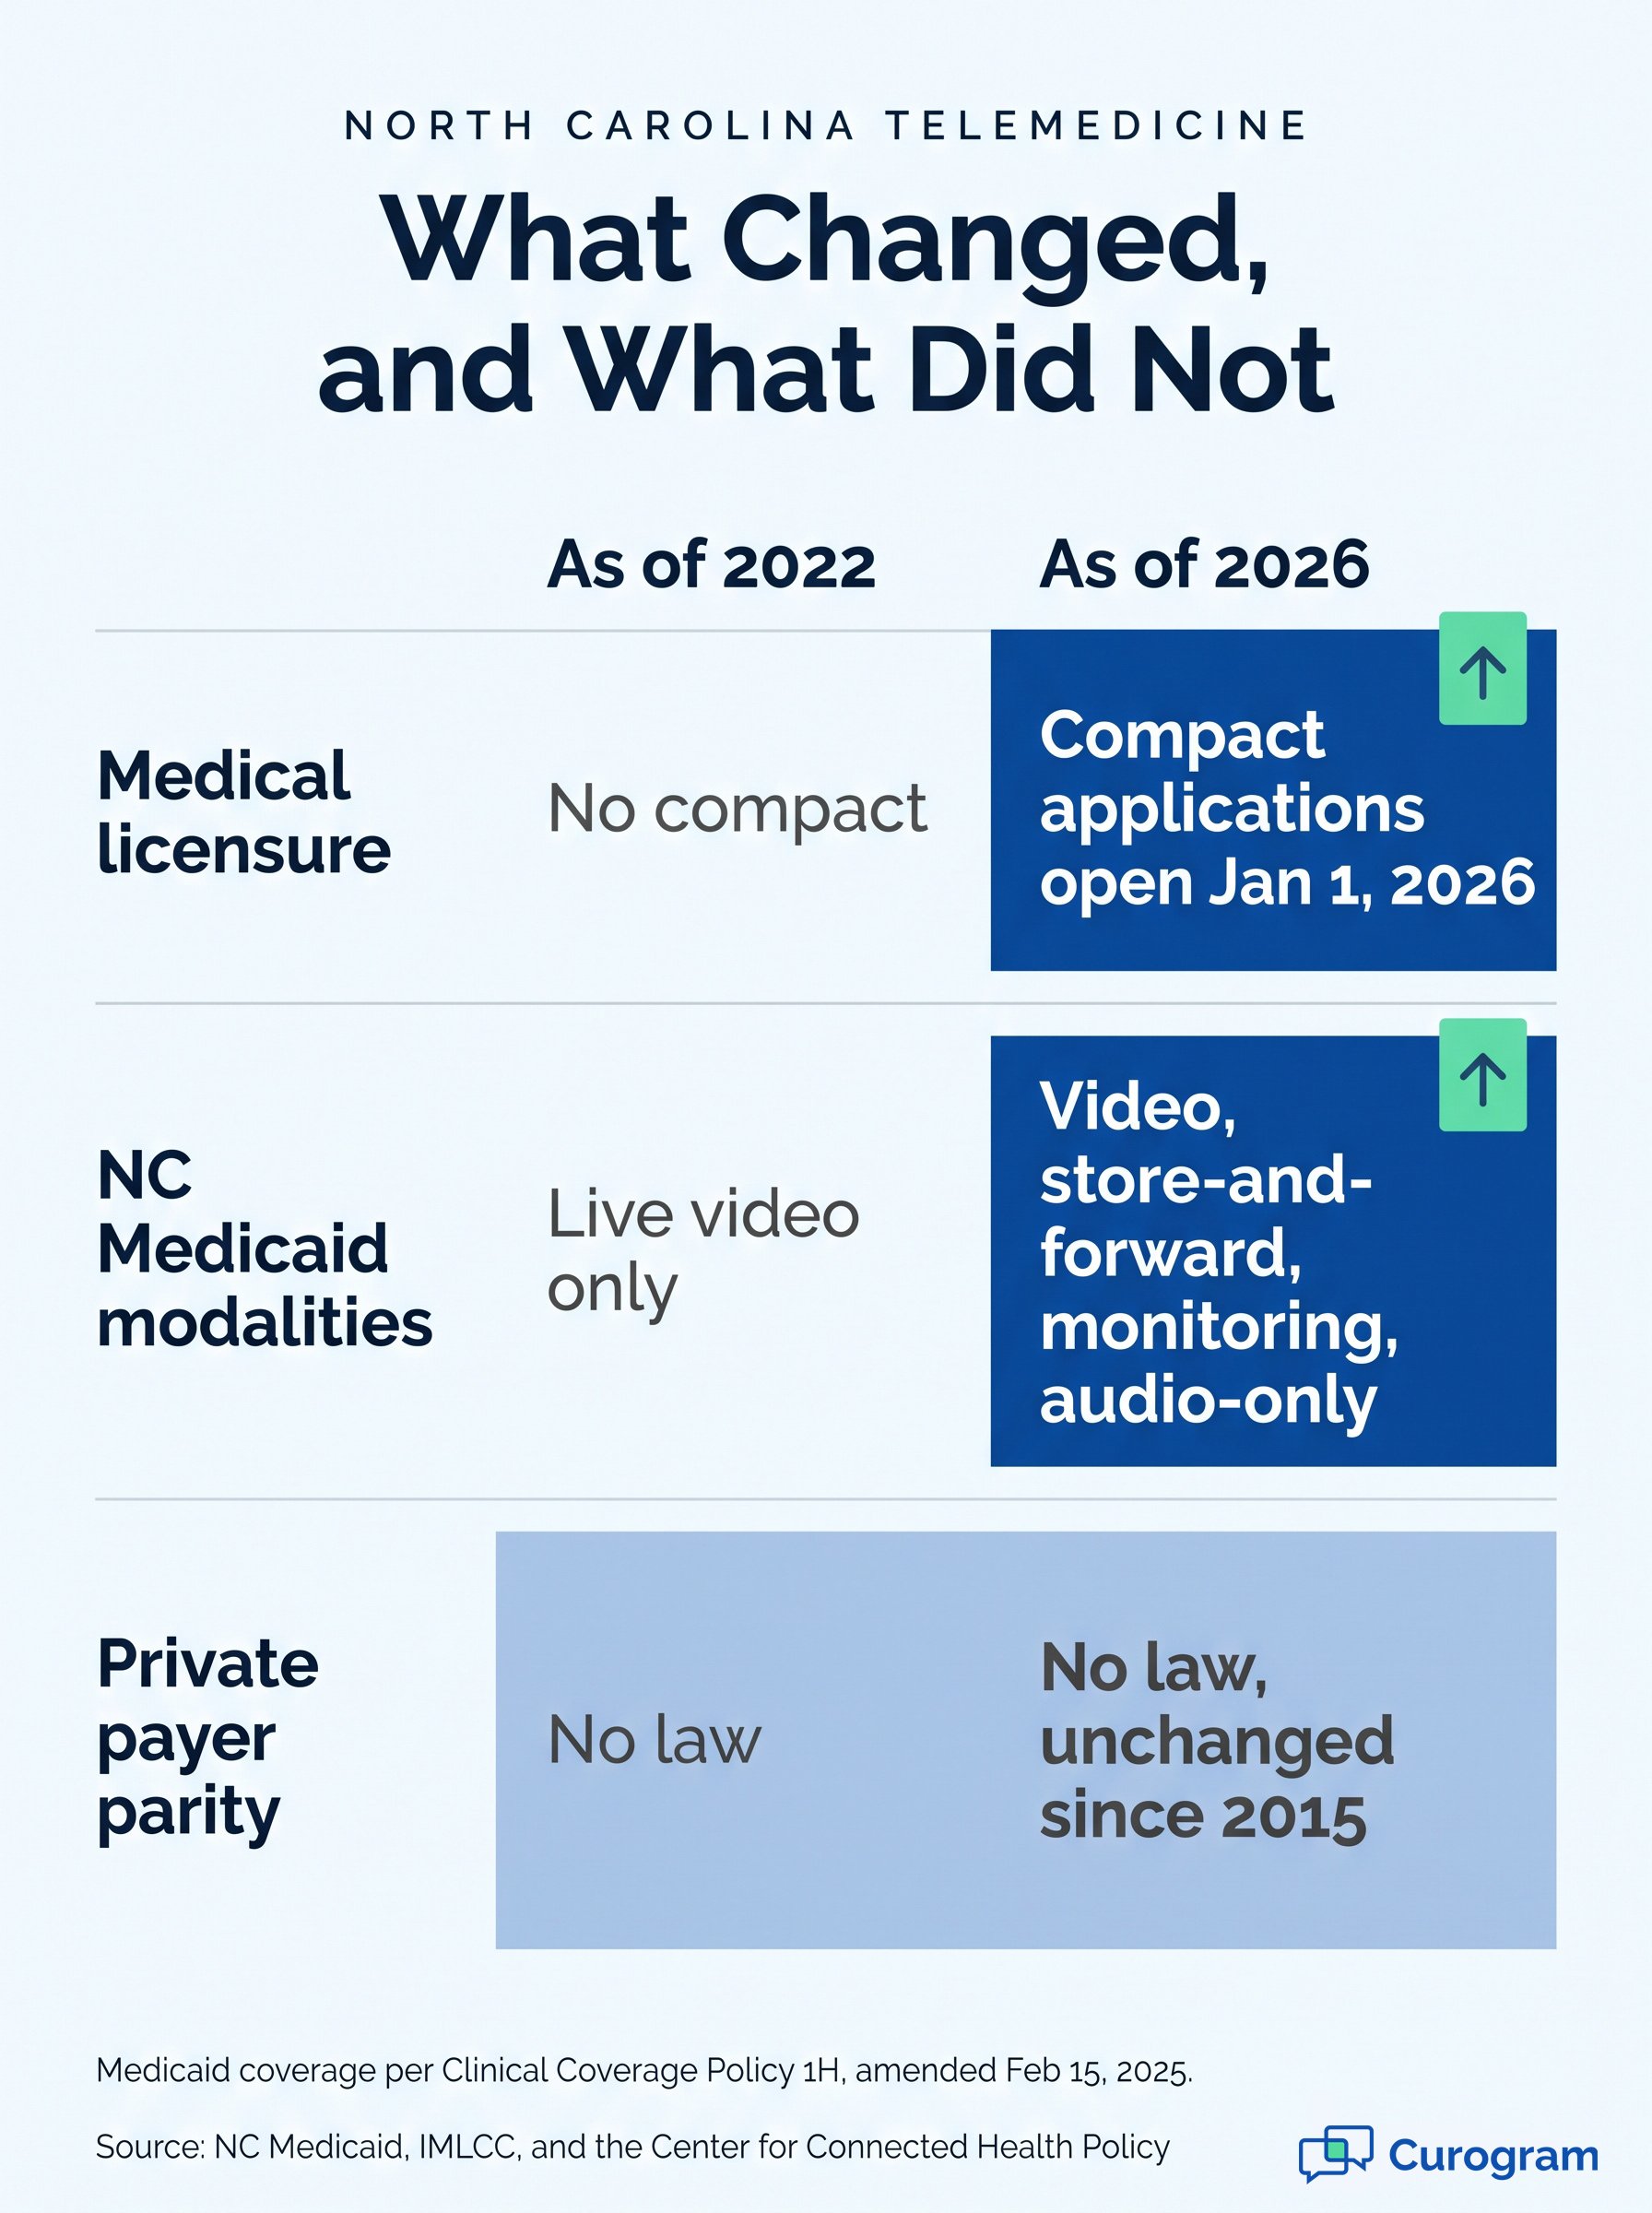
North Carolina has now joined the Interstate Medical Licensure Compact. The medical board began accepting compact applications on January 1, 2026, after legislation passed in July 2025.
A doctor with a letter of qualification in another member state can ask for an NC license through the portal. NC doctors can use the same route the other way, across 44 states and territories.
Tell patients what a virtual visit cannot do, and what happens if the connection drops or the problem turns urgent. Name the backup plan in writing. A disclaimer that says call 911 and nothing else is not a plan.

Coverage and payment are two different questions here. The state answers them very differently.
This is the gap that has not moved. The Center for Connected Health Policy records no private payer telehealth law in North Carolina. There is no payment parity law either.
Bills have been filed since 2015 without passing. Commercial coverage is therefore a contract question, not a statutory one.
Check your three largest commercial contracts directly. Assuming parity because a neighboring state has it is how a practice ends up writing off virtual visits.
Here the old version of this page is out of date. NC Medicaid policy 1H covers telehealth, virtual communications, and remote patient monitoring, amended February 15, 2025. Live video is covered. So is store-and-forward, so is remote patient monitoring, and so are synchronous audio-only codes.
Eligible provider types are broader than they were. Attachment A lists physicians, nurse practitioners, psychiatric nurse practitioners, and physician assistants. Certified nurse midwives and clinical pharmacist practitioners are on it too. The mix varies by code family.
Behavioral health sits under its own policies rather than 1H. Check 8C before assuming a code behaves the same way.
Two forces are pushing in the same direction, and one brake is still on.
North Carolina launched Medicaid expansion on December 1, 2023. NCDHHS reported more than 600,000 people enrolled within the first year. That population skews rural and working age. Those are the patients for whom a half day off work is the real cost of a visit.
Curogram Highlight: The Join is the Whole ProblemCurogram's Virtual Visits open from a text link in the phone browser. No download, no account, no password to reset while the clinician waits. That matters more in a county with thin broadband than in Charlotte. Curogram's telehealth software connects with 70+ EMR and practice management systems, so the link goes out with the reminder. Curogram is HIPAA compliant and SOC 2 Type II certified. Specialty practices including those running telehealth in Cloud 9 software use the same flow. |
State lines still decide who you may treat, and North Carolina now sits inside more compacts than most people realize.
The state is also in the nursing, psychology, and counseling compacts. Physical therapy, occupational therapy, physician assistant, and social work are in there too.
Each one runs on its own rules and its own application. Compact membership speeds up licensure; it does not remove it.
The patient's location still governs. A North Carolina physician treating a patient sitting in Virginia needs Virginia authority, compact or not.
Two things on this page were true in 2022 and are not true now.
The state is now in the medical compact. NC Medicaid pays for stored images and remote checks as well as live video.
One thing has not changed at all. There is still no private payer parity law, so commercial payment rests on what your contracts say.
Start by reading policy 1H against the codes you actually bill. Then pull your three largest commercial contracts and find the telehealth language.
After that, fix the join. None of the coverage matters if the patient in Ashe County cannot get into the visit.
See what a virtual visit looks like when the patient taps one link and nothing else. Book a Curogram demo.
 Michael Hsu : 6/19/20, 10:40 AM
Looking to capture the telehealth market? Here are the best methods that will help you practice telemedicine in Virginia profitably and successfully.
 Michael Hsu : 6/15/20, 9:19 AM
Starting to practice telemedicine in Georgia? Learn how the top providers in Georgia are deploying telemedicine practices profitably and efficiently.
 Michael Hsu : 6/20/20, 10:49 AM
The provider's ultimate guide to telemedicine in Maryland. Learn how to streamline your telehealth business and keep ahead of the competition.