
 Michael Hsu
Telemedicine Virginia: A Comprehensive Guide
 Michael Hsu : 6/19/20, 10:40 AM
Looking to capture the telehealth market? Here are the best methods that will help you practice telemedicine in Virginia profitably and successfully.

Much of the Idaho telehealth guidance still online describes the state as it stood in 2020. It says Idaho has no telehealth law, no definitions, and no clear path for out-of-state providers. Every one of those claims is out of date.
Idaho first wrote telehealth into law in 2015. In July 2023, it replaced that law with the Virtual Care Access Act.
The new Act lets you start a patient relationship by video, gives out-of-state providers six ways to treat Idaho patients without an Idaho license, and holds every virtual visit to the same standard as an office visit. Idaho Medicaid now pays for video, phone, and remote monitoring at the in-person rate.
The rules are clear now. What still trips Idaho practices up is the work around them: the claim denied because a call dropped, the commercial plan that pays less for video, and the visit notes retyped into the EHR after hours.
This guide covers both sides. You’ll find what Idaho law requires today on licensing, consent, records, prescribing, and data security. You’ll also see where payment works, where it doesn’t, and what to look for in a platform so your front desk isn’t the one patching the gaps.
If your practice already offers virtual visits, use it to check your current setup against the 2023 rules. If you’re just starting, it gives you the order to set things up in.
Telemedicine is when a doctor or another licensed provider cares for a patient from a remote site. The two connect through a phone or computer instead of sharing an exam room.
The visit can happen over live video, secure chat, email, or text. Your provider can still examine, diagnose, and treat the patient. Nobody has to sit in the waiting room.
Every in-person visit carries admin and logistics costs, from checking patients in to turning over rooms.
Telemedicine cuts much of that work, so your providers spend more of their day on patient care. You can put that saved time toward added services, which means patients get more care for the same cost.
Medicaid and Medicare both cover some remote care. That coverage matters most for patients who already struggle to pay their medical bills.
COVID-19 sped up how fast practices adopted telemedicine. A video visit kept patients out of shared waiting rooms and was often quicker to book. Many patients also found it easier to use than they expected.
People often use these two words to mean the same thing. They overlap, but telehealth is the wider term.
| Telemedicine | Telehealth | |
|---|---|---|
| What it covers | Remote medical care, such as a diagnosis or treatment plan | Remote medical care, plus non-clinical services tied to health and well-being |
| Example | A video visit to adjust a blood pressure medication | That same visit, or a nutrition class held online |
Some states treat the two terms as separate in their laws. Idaho doesn’t. Its law uses one term, “telehealth services,” and defines it as care a provider gives a patient at another site.
That care can happen through electronic messages, information technology, store-and-forward transfer, or a live session.
Idaho first wrote that definition into the Telehealth Access Act of 2015. In July 2023, the law was updated and renamed the Virtual Care Access Act. If you treat a patient who is located in Idaho, its rules apply whichever term you use for the visit.
Idaho isn’t the most active state on telehealth law, but plenty of physicians and practices offer remote visits to patients across the state. The rules they follow now sit mainly in one statute.
| Area | Idaho’s status |
|---|---|
| Telehealth law | Yes. It’s the Virtual Care Access Act, which updated the 2015 Telehealth Access Act in July 2023. |
| Private payer parity law | No |
| Board of Medicine telehealth rules | Withdrawn |
| Medicaid telehealth coverage | Yes, for some services |
The biggest open issue is pay. Idaho has no private payer parity law, so commercial insurers don’t have to cover telehealth visits or pay the same rate as an in-person visit.
Insurers can still choose to cover them. Many paid full in-person rates during the pandemic, but no state law makes them keep doing so. Before you book a video visit, check each payer’s current telehealth policy.
The Idaho Board of Medicine (IBM) wrote some of the first telehealth guidelines for providers and patients. Those rules were later withdrawn as part of a statewide effort to cut regulations.
The Idaho Medicaid branch set its own telehealth policies and pays for some remote care. For many Idahoans on Medicaid, that coverage is what makes a video visit possible.
The Idaho Board of Medicine (IBM) worked from one idea: a video visit should meet the same bar as an office visit. It took the rules that already covered in-person care and applied them to telemedicine. The goal was to keep patients safe and hold the quality of care steady.
That idea outlasted the Board’s own rules. Idaho law still holds you to the Idaho community standard of care for every telehealth visit. It’s the same standard you’re measured against in the exam room.
| Focus area | What it means for your visits |
|---|---|
| Doctor-patient relationship | Set it up properly before you diagnose or treat |
| Data privacy | Protect patient information as closely as you protect your office records |
| Evaluation and treatment | Assess the patient as fully as you would in person |
| Prescribing | Prescribe with the same care you’d use in the office |
Every Idaho telehealth rule builds on the doctor-patient relationship. A video visit has to meet the same standard you’d meet in your office.
That starts with a real evaluation. Before you diagnose or treat, Idaho law requires you to collect and document the patient’s history and current symptoms.
A static online questionnaire on its own doesn’t count. Some patients will still need an in-person visit, and telehealth works best as one option among your services.
Idaho doesn’t require a first meeting in person. The relationship can start on a video call or through another virtual tool, as long as your care meets Idaho’s community standard.
Once you agree to diagnose and treat the patient, and the patient agrees to care this way, the relationship counts.
You may not need your own relationship with the patient at all. If a colleague in your provider group already treats them, or you’re covering calls for their provider, you can step in.
At the first virtual visit, cover these three steps:
When you can, let the patient choose which provider they see.
Your license has to match where the patient is during the visit. Idaho counts a virtual visit as taking place at the patient’s location, not yours.
| Where you are | Where the patient is | License you need |
|---|---|---|
| Idaho | Idaho | Idaho |
| Idaho | Another state | That state’s, under its rules |
| Another state | Idaho | Idaho, unless an exception applies |
Since July 2023, providers licensed in good standing in another state can treat Idaho patients without an Idaho license in six cases:
Out-of-state mental and behavioral health providers have one more route. They can register with Idaho every two years to offer telehealth there. Any exempt provider still answers to Idaho law, its community standard of care, and its licensing boards.
Once licensing is settled, telehealth carries the same laws, rules, and paperwork as in-person care. Four duties come up at every virtual visit:
Get the patient’s informed consent before you examine or treat them. Idaho law requires it for virtual care, the same as for an office visit.
Under Idaho’s Medical Consent Act, consent is informed when the patient understands three things. They need to know why they need the care, what it involves, and its main risks.
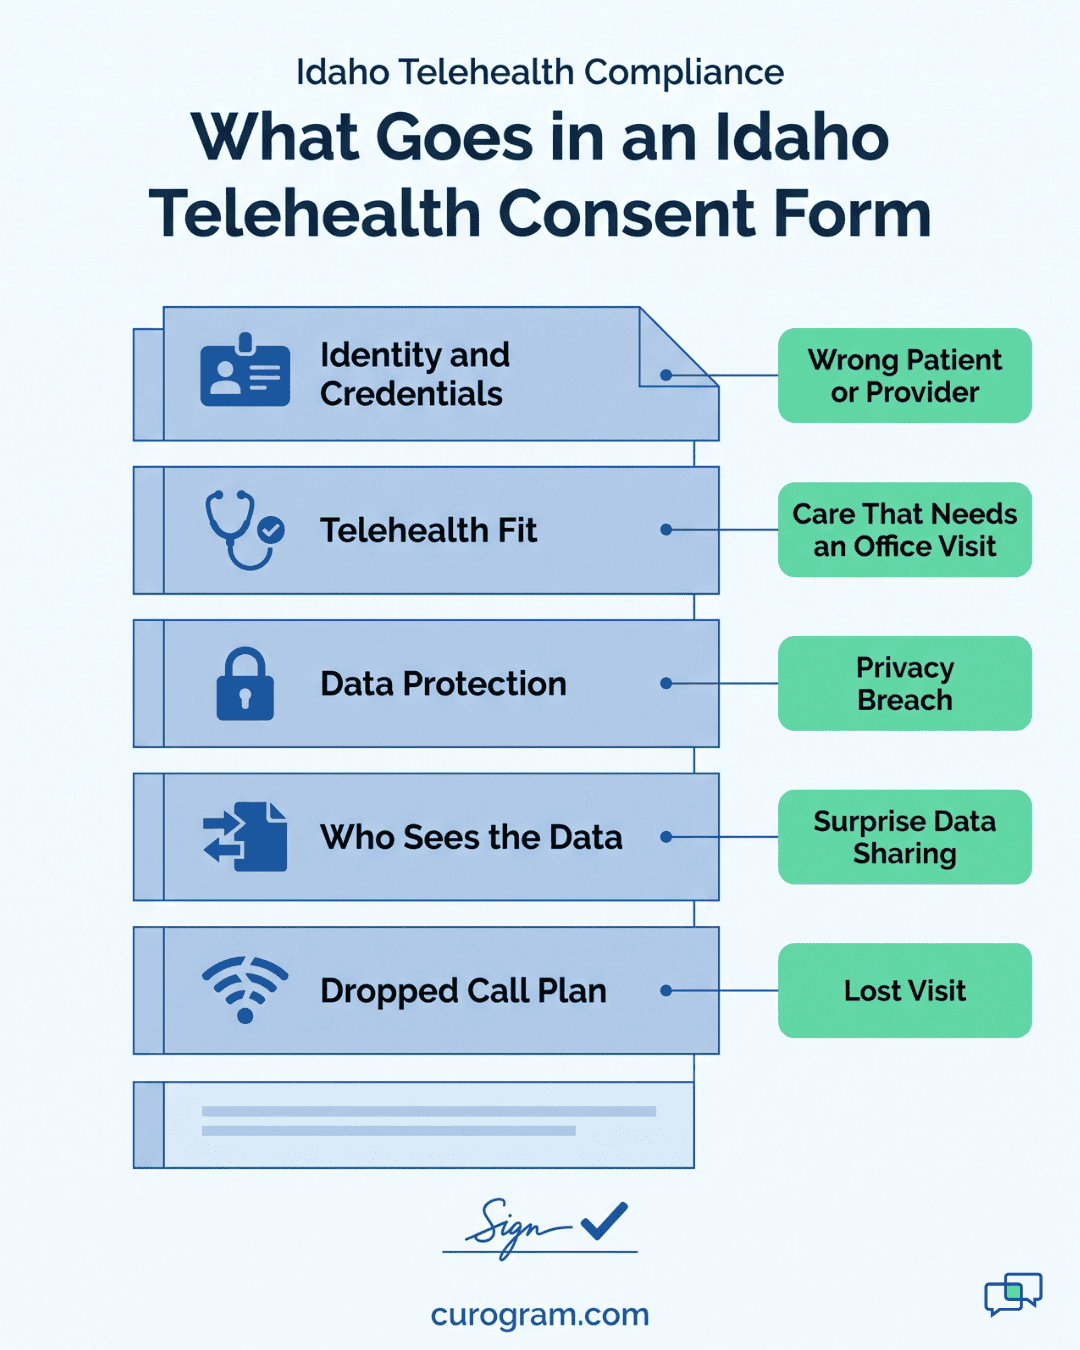
The law doesn’t prescribe a telehealth consent form. Even so, a signed, written record gives you proof that the patient agreed and shows what they were told. Idaho’s earlier Board of Medicine guidance listed what that record should cover:
Health law firm Holland & Hart also suggests covering two telehealth-specific points. Tell the patient the limits of a virtual visit, and explain what happens if the connection drops mid-session.
A virtual visit doesn’t end your duty to the patient. Under Idaho law, you or another provider in your group must be available for follow-up care. If you can’t provide it, you have to tell the patient how to get it elsewhere.
Every telehealth patient also needs a clear way to reach their provider of record, such as a phone line, a portal, or a text number. Their records should be easy for them to get, too, including their history, prescriptions, and test results.
Emergencies take more planning. When a patient needs care that a screen can’t give, you must refer them, including to emergency services. That means knowing the options where the patient is, not just near your office.
For example, a Boise provider seeing a patient in Salmon should know which emergency room and urgent care serve Salmon before the call starts. Keep a written emergency plan with these contacts and your steps for handing off care.

Chart a telehealth visit the way you’d chart an office visit. Idaho law holds virtual care records to the same standard as in-person ones. They must also follow federal privacy laws, including HIPAA and HITECH.
A complete record for a virtual patient covers two kinds of material:
Patients have the right to see their own records. Other providers can see them only if the patient gives permission. A specialist you refer to, for example, needs that okay before you share the chart.
A telehealth visit sends patient data across phone lines, Wi-Fi, and outside servers. The same federal and state privacy laws cover that data as cover a paper chart. Idaho’s Virtual Care Access Act names HIPAA and HITECH directly for virtual care records.
| Your duty | What it looks like in practice |
|---|---|
| Keep records secure | Store virtual visit notes, messages, and recordings with the same retention rules as in-person records |
| Protect confidentiality | Hold video visits where others can’t overhear, on both your side and the patient’s |
| Use a compliant platform | Choose a tool that encrypts data and gives each staff member their own login |
| Sign a BAA | Get a business associate agreement from every vendor that handles patient data |
During the pandemic, federal regulators let practices use everyday apps like FaceTime and Skype without penalty. That grace period ended in August 2023. If your providers still run visits on a consumer video app, it’s time to switch.
For many patients, your website is the first place they decide whether to trust a virtual visit. Idaho’s earlier Board of Medicine guidance set out what a telehealth site should show. Those rules have since been withdrawn, but the list still works as a trust checklist.
| What patients want to know | What your site should show |
|---|---|
| Who will treat me? | Services offered, provider contact details, and every provider’s credentials and licenses |
| What will it cost? | Fees, accepted payment methods, and any added costs |
| How does it work? | Simple steps for using the site and visit tools, plus how fast you reply on each channel (portal, text, phone) |
| Who sees my data? | Any third party with access to patient information |
| What are my rights? | Patient rights and how to use them |
Patients should have easy access to their own records and documents, which Idaho law requires.
Give them a clear way to leave feedback and file a complaint with the right medical board, either on the site or in your app. List who runs the site, its domain, its location, and contact details.
Keep the site free of ads. Skip any promotion of products or services that would earn your providers money. Links to educational resources are fine, as long as no provider profits from them.
A prescription written after a video visit follows the same rules as one written in your office. Under Idaho’s Virtual Care Access Act, you can prescribe drugs or medical devices through telehealth when all four of these are true:
A static online form doesn’t count as an exam. Treating a patient based only on a questionnaire falls short of Idaho’s standard of care.
Controlled substances need extra care. Federal rules that let you prescribe them by telehealth without a prior in-person visit have been extended through 2026. Check the DEA’s current status before you rely on them in 2027.
Idaho’s earlier Board guidance added two habits that still make sense. Let the patient choose their pharmacy, with no “preferred” pharmacy pushed on them. Send prescriptions through an e-prescribing system to cut errors from handwriting and phoned-in orders.
Idaho’s rules on licensing, consent, records, and prescribing add steps to every virtual visit. Even so, the medicine is rarely what trips practices up. The trouble usually starts with the technology.
The failures are familiar:
Each one costs trust. Patients have to trust both the provider and the channel. That means your tool needs to meet every privacy rule and still be simple enough to join without calling your office. Your choice of platform decides whether telehealth works for your practice.
Curogram gives you secure, encrypted telehealth tools, so your providers spend visits treating patients, not fixing connections.
Before you commit to a telehealth tool, check it against three tests:
The EHR test matters most, because your providers and patients both depend on what’s in the chart.
When the platform syncs with it, your front desk stops doing double entry and spends less time chasing missing details. Based on our internal data, practices see a 30%+ lift in front desk productivity once routine patient communication runs through Curogram.
Curogram connects with major EHRs, so visit data flows into the chart without retyping. Your providers get time back for patient care and can fit more patients into the day. Here are some Curogram EHR integrations:
Patients judge a virtual visit on three things:
If the tool feels confusing, patients put off the visit or call your front desk for help. Text is the channel most patients can use without any setup, which is why two-way texting carries so much of the load.
Two-way texting. Your reminders go out automatically, and patients reply to confirm or reschedule. Based on our internal data, practices on Curogram keep a confirmation rate above 75%. Atlas Medical Center cut its no-show rate from 14.20% to 4.91% in three months.
Fewer calls to the front desk. When patients can text back, they stop calling to ask about times or links. Our internal data shows a 24% drop in inbound calls from automated texting.
Private messages between staff. Nurses, providers, and the front desk can send messages and share files inside a secure channel instead of using personal phones.
Virtual clinics and waiting rooms. These follow your in-person flow. Your staff can check patients in and prepare them before the visit, and the provider starts the video call once the patient is ready.
EHR sync. Curogram connects with major EHRs, so what a patient tells you by text or video lands in their chart.

Getting paid is still the hardest part of telehealth in Idaho. The state has no parity law, so what you collect depends on who covers the patient.
| Payer | What to expect |
|---|---|
| Commercial insurers | Coverage and rates vary by plan, and no state law sets them |
| Idaho Medicaid | Pays for certain telehealth services |
| Medicare | Federal telehealth flexibilities run through December 31, 2027 |
A parity law doesn’t look close. Idaho’s telehealth task force decided a mandate wasn’t the best path and urged insurers to treat parity as a “best practice” instead. The head of the state agency also said his office has no legal power to require it.
For your billing team, that means checking each commercial payer’s telehealth policy before the visit, not after the claim comes back.
Rural patients gain the most from telehealth. They can see the provider they choose without a long drive, and you can fit more patients into a full day.
Cost is the other big draw, especially for patients on a tight budget. Idaho Medicaid pays for virtual care at the same rate as an in-person visit, so treating a Medicaid patient by video doesn’t cost you anything on the claim.
| Visit type | Does Idaho Medicaid pay? |
|---|---|
| Live video | Yes |
| Audio-only (phone) | Yes |
| Remote patient monitoring | Yes, for established patients |
| Store-and-forward | No |
Any service Medicaid already covers can be done virtually when it meets four conditions:
That rule covers primary care, specialty visits, psychiatric diagnostics, crisis intervention, psychotherapy, and medication management.
Eligible providers now include healthcare providers in general. That’s broader than the old list of physicians, nurses, physician assistants, midwives, clinical psychologists, physical and speech therapists, and early intervention specialists.
Watch for three billing details:
Telehealth also cuts down admin work, so your staff spends more time on patients and less on paperwork. During COVID-19, practices running testing sites used Curogram to mass text testing invites and take replies by text, which kept their phone lines open for other calls.
Don’t see your state? We just haven’t written about it yet! Stay tuned on our blog or check out our article on telemedicine reimbursement by state.
|
Nebraska |
|||
|
Alaska |
Iowa |
Nevada |
South Dakota |
|
Kansas |
New Hampshire |
||
|
Kentucky |
|||
|
New Mexico |
Utah |
||
|
Maine |
Vermont |
||
|
Connecticut |
|||
|
Delaware |
North Dakota |
||
|
West Virginia |
|||
|
Oklahoma |
|||
|
Mississippi |
Wyoming |
||
|
Montana |
Rhode Island |
See how it would work in your practice. Schedule a demo and we’ll walk you through Curogram with your own workflow, from the first reminder text to the final chart note.
 Michael Hsu : 6/19/20, 10:40 AM
Looking to capture the telehealth market? Here are the best methods that will help you practice telemedicine in Virginia profitably and successfully.
 Michael Hsu : 6/22/20, 11:03 AM
The provider's ultimate guide to telemedicine in Wisconsin. Learn how to streamline your telehealth business and keep ahead of the competition.
 Michael Hsu : 6/10/20, 8:52 AM
Learn how California's top health providers launched profitable, streamlined, and compliant telehealth services in our guide to telemedince in...