
 Michael Hsu
1 min read
Telemedicine Virginia: A Comprehensive Guide
 Michael Hsu : 6/19/20, 10:40 AM
💡 Telemedicine is legal and widely covered in Virginia, but three rules decide whether a visit is valid and paid.First, licensing follows the...

California wrote telemedicine into state law in 1996. That's before most medical practices even had a website.
You'd think the rules would be settled by now. They aren't. The state has passed new telehealth laws every few years since then, and the pace picked up after COVID-19. Each change shifted what's covered, who gets paid, and what you need to document.
That puts your practice in a tricky spot. The rules for a video visit in 2020 aren't the rules you follow today. A phone visit that Medi-Cal paid for during the emergency may now need a different modifier. A consent script that once worked may now be missing a required disclosure.
Small gaps like these add up fast. A missing consent note can become an audit finding. A wrong modifier can become a denied claim. Repeat that across dozens of virtual visits a week, and the lost time and money get real.
Here's the good news. California is still one of the most telehealth-friendly states in the country. Private plans must pay for telehealth on the same basis as in-person care.
Medi-Cal covers video, phone, and store-and-forward visits. And you don't need to see a patient in person before you treat them remotely.
The state didn't get here by accident. For decades, California faced gaps in access to care, an aging population, and a shortage of medical professionals. By the 1990s, it was looking to telemedicine as a real answer to all three. Lawmakers have kept building on it ever since.
In this guide, you'll see how telemedicine in California grew over time and what the law asks of you today. We'll cover who can provide care, licensing limits, consent, prescribing, documentation, and billing. By the end, you'll know what your practice needs to deliver remote care with confidence.
To better understand the current state of telemedicine in California, here’s a timetable of all the relevant events that led to the state having one of the most comprehensive telemedicine legislatures in the United States.
California’s first step into the field of telemedicine occurred back in 1992 when the University of California — Davis launched a telemedicine program for the purpose of fetal monitoring in rural areas.
Quickly recognizing the value of telemedicine, Kaiser Permanente in Sacramento launched a home telemedicine program, aimed at providing other forms of medical care remotely. Blue Shield of California and the state’s prison system were also among the first to recognize the benefits of telemedicine and develop their own programs to further improve the accessibility of remote healthcare services.
The state’s legislators quickly caught wind of the growing demand of telemedicine and sought to define the practice under law. The Senate Bill 1665 — better known as The Telemedicine Development Act — was enacted in 1996.
The main goal was to further improve access to telemedicine. The Development Act accomplished this by imposing a specific requirement for health insurers. The Act stated that health plans were forbidden from requiring face-to-face contact between the providers and the patients for services delivered remotely.
This meant that:
This made telemedicine more appealing to both patients, who didn’t have to worry about additional medical fees, and clinical practices, that could treat more patients by implementing virtual appointments.
That said, the Act did require healthcare professionals to obtain written patient consent prior to delivering any services via telemedicine.
As technology advanced, it became obvious that the existing law needed to be updated to clarify previous definitions surrounding telemedicine and telehealth and provide new ones. The Bill replaced the term “telemedicine” with “telehealth.”
The old legal terminology described telemedicine exclusively as delivering treatment through a two-way live video connection. With technological advancements, the rigid term proved to be a barrier to other forms of remote medical services.
The Advancement Act included store-and-forward technology as another form of reimbursable telemedicine service. This enabled providers to rely on telecommunication technology to share medical information when necessary, such as lab test results, and greatly facilitated telemedicine services.
The biggest change that The Telehealth Advancement Act made was the fact that the law now mandated private payers to reimburse healthcare providers for telemedicine services. Prior to this, telemedicine services were only delivered to patients in licensed healthcare facilities.
Although there were no explicit restrictions regarding the location where telemedicine takes place under the old law, Medi-Cal did limit telemedicine to four types of facilities:
The majority of private payers misinterpreted that Medi-Cal’s limitations apply universally, resulting in telemedicine being delivered exclusively to these types of facilities.
The Advancement Act clarified this and explicitly removed any location restrictions. The mandate dramatically increased the appeal of telemedicine for providers, given that they could deliver remote healthcare service to patients regardless of their location — even in their homes.
The AB 1733 introduced several modifications to California’s telehealth policy.
The most notable changes were:
In addition, the Bill allotted $200 million for the improvement of medical education programs that were aimed at developing high-tech approaches to medical care delivery.
This marked the state’s commitment to telehealth and signified that California values remote healthcare services as much as medical aid delivered in-person.
The Bill 809 removed the previous requirement for written patient consent. This requirement complicated entering relationships with new patients via telemedicine, and was removed as it proved to be an unnecessary hindrance.
Today, providers can obtain either verbal or written consent prior to delivering telemedicine services but must document and keep proof of consent for any patient that receives any form of remote medical care.
In 2019, Governor Gavin Newsom signed multiple Bills that marked California the most pro-telehealth state in the U.S.
Assembly Bill 744 — This bill mandated that payers would reimburse healthcare providers for telemedicine services “on the same basis and to the same extent” as they would for in-person services.
This positioned telehealth as equally valuable to in-person medical treatment, and payers could no longer “haggle” for lower coverage rates for telehealth services.
Assembly Bill 1264 — The main objective of this Bill was to facilitate online prescriptions. It defined “asynchronous communication between the patient and the provider” as a valid way of establishing a doctor-patient relationship, which is a requirement for any type of medication prescription.
Put simply, this Bill allowed telehealth providers to issue online prescriptions without requiring the patients to come in for an in-person evaluation.
Assembly Bill 1494 — The Bill enabled healthcare providers to leverage telehealth to provide medical services to Medicaid patients during and immediately after an emergency. Telephone consultations were included in said services.
Assembly Bill 24 — The Bill mandates that, as of 2023, healthcare clinics on California State University or University of California campuses must provide access to telemedicine abortion services.
State law doesn't limit which licensed pros can give remote care. If you hold a valid California license, you can use telehealth for any care your license allows.
Medi-Cal is the state's Medicaid program. It takes a similar view. Common types of providers who bill it for telehealth include:
For your team, this means most of your care staff can see patients from afar. Each person just needs a California license and to be signed up with the right payers.
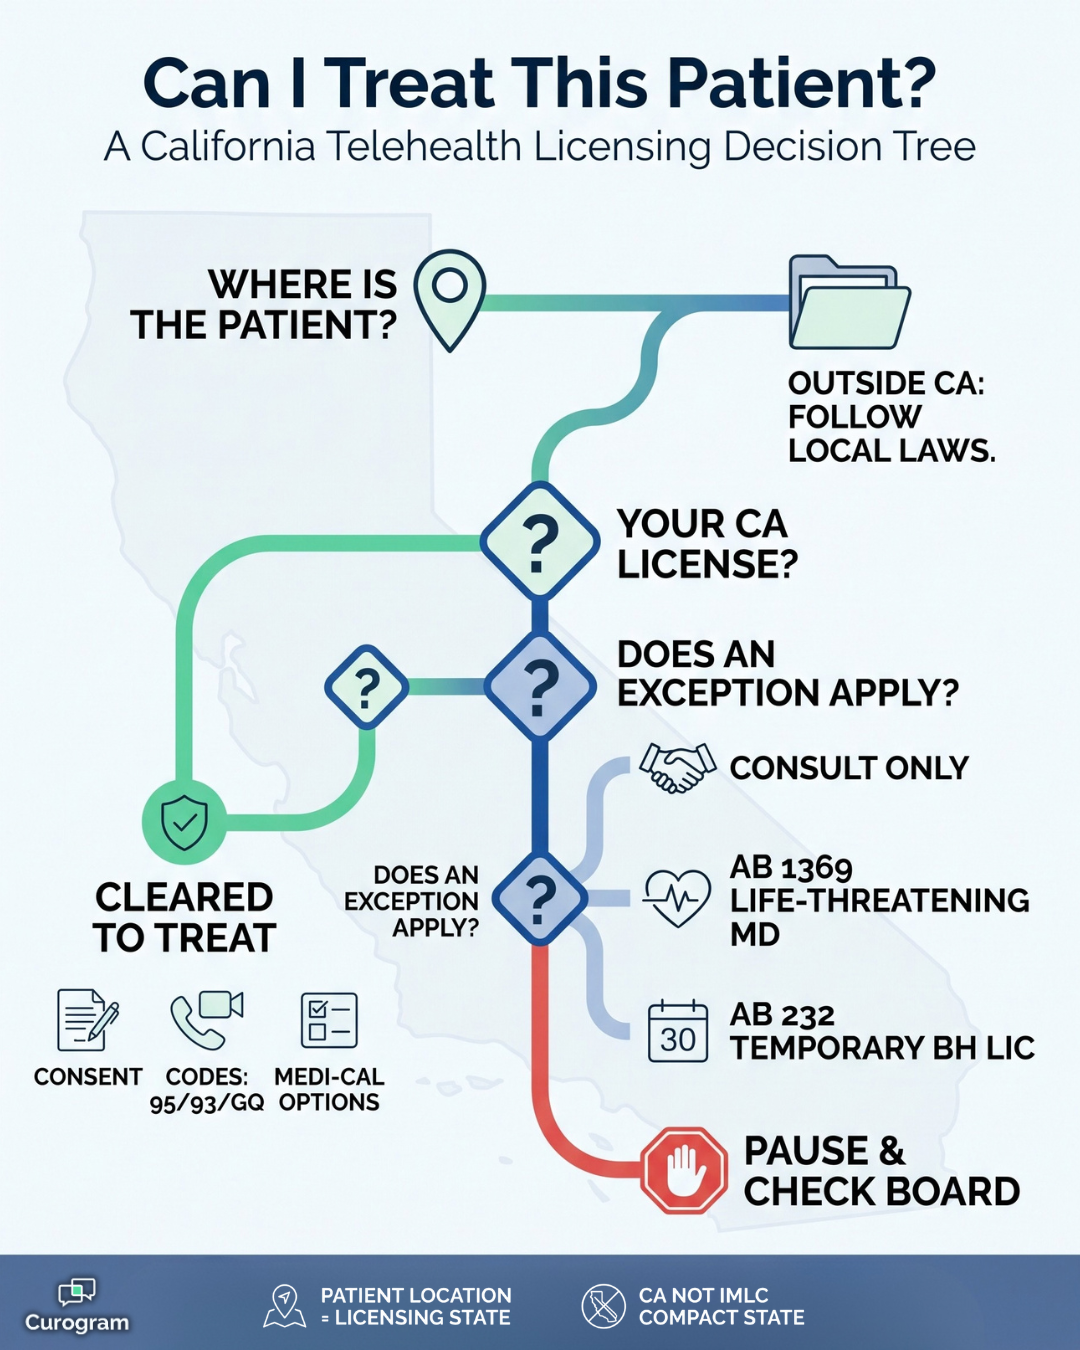
California backs telehealth, but it hasn't joined the Interstate Medical Licensure Compact. That deal makes it easier for doctors to get licensed in member states.
What counts is where the patient is, not where you are. To treat a patient in California, you most often need an active California license.
There are only a few narrow exceptions:
| Exception | Who it covers | What it allows |
|---|---|---|
| Provider-to-provider consults | Out-of-state physicians | Advising a California-licensed provider who stays in charge of care |
| AB 1369, the David Hall Act (2023) | Out-of-state physicians | Telehealth for patients with an immediately life-threatening disease or condition, under set conditions |
| AB 232 (2023) | Out-of-state behavioral health licensees | A 30-day temporary practice allowance approved by the Board of Behavioral Sciences |
If a case doesn't clearly fit one of these, check with the Medical Board of California or your licensing board before the visit.
Written consent hasn't been required since 2015. That fits the state's view that an in-person visit isn't needed to build a valid doctor-patient relationship.
Under state law, you must tell the patient you plan to use telehealth and get their verbal or written consent before the first telehealth visit. Then you record that consent in the patient's chart.
Medi-Cal asks for a bit more. Before the first telehealth visit, you need to tell Medi-Cal patients:
The duty to get consent falls on the provider who starts the telehealth process. So if a patient at your clinic needs a remote specialist, your team may be the one that needs to get consent first.
California is fairly flexible about prescribing through telehealth. If you can deliver telehealth and you have prescribing rights, you can prescribe to patients you see remotely.
Thanks to AB 1264, the exam California requires before you prescribe can happen through telehealth.

Before you send a remote prescription, run through three quick questions:
If any answer is "no" or "I'm not sure," an in-person visit may be the safer choice.
California law doesn't set separate rules for documenting telehealth visits. But since AB 744 treats telehealth like in-person care, you should record and store notes just as you would for an office visit.
In practice, that means updating your electronic health record (EHR) after every virtual visit. HIPAA rules also call for a backup plan, so you can still reach patient data in an emergency like a power outage.
Keep both points in mind when you choose a telehealth platform. If it doesn't connect to your EHR, your staff will have to type in visit details by hand. If it doesn't include backups, you'll need to find a separate HIPAA-compliant vendor for that.
We built Curogram with these gaps in mind. It's a platform designed to help medical teams use secure, modern communication tools to care for patients remotely.
Curogram integrates with your EHR, so visit data flows into your records automatically. Your staff spends less time on data entry and more time on patients. The platform also comes with automatic data backup and built-in safeguards that support HIPAA compliance.
|
Curogram EHR integrations |
|
|
eClinicalWorks |
Athena |
|
Epic |
Cerner |
|
DrChrono |
NextGen |
|
Practice Fusion |
CareCloud |
|
Kareo |
OfficeAlly |
| Before your next California telehealth visit, confirm four things |
|---|
| First, the patient is physically in California and you hold an active California license. Second, the patient's consent is recorded in the chart. Third, the claim carries the right modifier: 95 for video, 93 for phone, or GQ for store-and-forward on Medi-Cal claims. Fourth, if the patient has Medi-Cal, you've offered an in-person visit or a referral. Missing just one of these can lead to a denied claim or a compliance gap. |
California's payment parity law, AB 744, took effect in 2021. Under it, private health plans must cover telehealth on the same basis and to the same extent as in-person care. They can't require an in-person visit first, and they can't limit coverage based on where the patient is.
Medi-Cal also pays for telehealth at the same rate as in-person care. Here's how the main types of visits compare:
| Visit type | Private plans | Medi-Cal | Medi-Cal modifier |
|---|---|---|---|
| Live video | Paid at parity when the service is covered | Paid at parity for new and current patients | 95 |
| Phone (audio-only) | Check your plan contract | Paid at parity; new patients only in limited cases | 93 |
| Store-and-forward | Part of the state's definition of telehealth | Covered, including e-consults | GQ |
Store-and-forward under Medi-Cal used to be limited to skin, eye, and dental care. Coverage is broader now, but check the Medi-Cal provider manual for your specific service. Medi-Cal also pays an originating site fee, plus a transmission fee for up to 90 minutes per patient, per day.
So what does parity mean in dollars? Here's an illustrative example. Say your practice does 40 telehealth follow-ups a week at $110 each. That's $4,400 a week, or about $228,800 a year.
Now imagine payers could pay 20% less for virtual visits. You'd lose about $45,760 a year for the exact same work. That's the revenue the state's parity law protects. It's also a big reason telemedicine in California makes financial sense.
During the pandemic, California eased many telehealth rules to keep care moving. Most of those short-term rules have ended. But many came back as permanent law in a new form.
Here's where things stand now:
The takeaway is clear. The emergency is over, but telehealth is here to stay. Your workflows just need to match the current rules.
Curogram brings video visits, patient texting, and staff messaging into one secure dashboard.
Here's what that looks like day to day:
| Feature | What it does for your practice |
|---|---|
| Connects to your EHR | Visit details flow into your EHR automatically. Your team skips double entry and has more time for patients. |
| Two-way patient texting | Send automated text reminders that patients can reply to with questions or to reschedule. One Curogram client cut its no-show rate from 14.2% to 4.91%. |
| Secure staff messaging and file sharing | Your team can message each other and share patient data in a HIPAA-compliant space. |
| Virtual waiting rooms | Medical assistants can check patients in and gather details before the visit. Doctors see when the patient is ready and start the video call in one click. |
Don’t see your state? We just haven’t written about it yet! Stay tuned on our blog or check out our article on telemedicine reimbursement by state.
|
Nebraska |
|||
|
Alaska |
Iowa |
Nevada |
South Dakota |
|
Kansas |
New Hampshire |
||
|
Kentucky |
|||
|
New Mexico |
Utah |
||
|
Maine |
Vermont |
||
|
Connecticut |
|||
|
Delaware |
North Dakota |
||
|
West Virginia |
|||
|
Oklahoma |
|||
|
Mississippi |
Wyoming |
||
|
Montana |
Rhode Island |
California has spent three decades building one of the strongest telehealth frameworks in the entire country. That's good news for your practice. You can treat new patients by video, get paid the same as you would in person, and reach people who might never make it to your office.
But strong laws come with real rules. You need a California license for patients in the state, plus recorded consent before the first virtual visit. You need the right modifier on every claim. And if you serve Medi-Cal patients, you need to offer an in-person option or a referral.
None of these requirements is difficult on its own. The challenge is getting them right every time, across every provider and every visit. That's where your technology matters.
The right telehealth platform should take work off your team's plate, not add to it. It should keep patient data secure, sync visit details with your EHR, and make a virtual visit feel as smooth as an office visit.
Curogram was built for exactly that. Our platform includes the safeguards HIPAA calls for, so you can focus on care instead of compliance worries. You can set up a virtual clinic and start hosting live, two-way video visits in under 24 hours.
Curogram also keeps you connected outside the visit. You can text new and current patients, work with your staff, and share patient data securely, all from one dashboard. Virtual waiting rooms help keep your day on schedule, just like your front desk does in person.
California's telehealth rules will keep changing. Your practice doesn't have to scramble every time they do. The right partner keeps you ready for what's next.
Curious how it would fit into your practice's daily workflow? Book a demo of Curogram's telehealth platform and get a quick, personal walkthrough.
Frequently Asked Question

1 min read
Michael Hsu : 6/19/20, 10:40 AM
💡 Telemedicine is legal and widely covered in Virginia, but three rules decide whether a visit is valid and paid.First, licensing follows the...

1 min read
Michael Hsu : 6/7/20, 8:39 AM
💡 Alabama telemedicine is legal and widely used. But the rules sit in many places, not one law. Alabama Medicaid has no precise definition of...

1 min read
Michael Hsu : 6/13/20, 9:03 AM
💡 Telemedicine in Arkansas is legal, and payers cover it. The state Telemedicine Act sets the rules. You need an active Arkansas license. You also...